



The concurrent use of renin–angiotensin–aldosterone system (RAAS) inhibitors, diuretics, and nonsteroidal anti-inflammatory drugs (NSAIDs), known as the “triple whammy (TW),” increases the risk of acute kidney injury (AKI). Sacubitril/valsartan has demonstrated favorable renal effects in heart failure populations; however, its impact under triple whammy exposure remains unclear.
MethodsThis single-center retrospective observational study included patients with heart failure receiving valsartan or sacubitril/valsartan in combination with diuretics who were newly prescribed an NSAID between May 2013 and July 2024. Changes in serum creatinine (SCr) within 30 days after NSAID initiation were compared between groups. Multivariable linear regression was performed to identify determinants of relative SCr change. Factors associated with AKI, defined as an increase in SCr ≥0.3mg/dL, were evaluated using multivariable logistic regression with Firth's penalized likelihood method to address sparse event counts.
ResultsA total of 168 patients were included (valsartan, n=71; sacubitril/valsartan, n=97). The sacubitril/valsartan group had a higher diuretic burden at baseline. Despite this, relative increases in SCr were significantly smaller compared with the valsartan group. In multivariable linear regression analysis, higher loop-diuretic-equivalent dose was independently associated with greater SCr elevation, whereas sacubitril/valsartan use was associated with smaller relative SCr increases. In Firth logistic regression analysis, higher loop-diuretic dose was independently associated with AKI, while sacubitril/valsartan use was not significantly associated with AKI.
ConclusionsUnder triple whammy exposure, sacubitril/valsartan was associated with smaller early increases in SCr compared with valsartan, while diuretic intensity emerged as a consistent determinant of renal deterioration. Although causality cannot be established, these findings highlight the importance of volume management and support further prospective investigation.
.
El uso concomitante de inhibidores del sistema renina-angiotensina-aldosterona (SRAA), diuréticos y antiinflamatorios no esteroideos (AINE), conocido como «triple whammy» (TW), aumenta el riesgo de lesión renal aguda (LRA). Sacubitrilo/valsartán ha mostrado efectos renales favorables en pacientes con insuficiencia cardíaca, sin embargo, su impacto bajo condiciones de TW no está claro.
MétodosEste estudio observacional retrospectivo de un solo centro incluyó pacientes con insuficiencia cardíaca tratados con valsartán o sacubitrilo/valsartán en combinación con diuréticos, a quienes se les prescribió un AINE de forma nueva entre mayo de 2013 y julio de 2024. Se compararon los cambios en la creatinina sérica (Cr) dentro de los 30 días posteriores al inicio del AINE entre los grupos. Se realizó un análisis de regresión lineal multivariable para identificar los determinantes del cambio relativo de Cr. Los factores asociados con LRA, definida como un aumento de Cr ≥0,3 mg/dL, se evaluaron mediante regresión logística multivariable con el método de verosimilitud penalizada de Firth.
ResultadosSe incluyeron un total de 168 pacientes (valsartán, n=71; sacubitrilo/valsartán, n=97). El grupo de sacubitrilo/valsartán presentó una mayor carga de diuréticos al inicio. A pesar de ello, los incrementos relativos de Cr fueron significativamente menores en comparación con el grupo de valsartán. En el análisis de regresión lineal multivariable, una mayor dosis equivalente de diuréticos de asa se asoció de forma independiente con mayor elevación de Cr, mientras que el uso de sacubitrilo/valsartán se relacionó con incrementos relativos menores. En el análisis de regresión logística de Firth, una mayor dosis de diuréticos de asa se asoció de forma independiente con LRA, mientras que el uso de sacubitrilo/valsartán no se asoció significativamente con LRA.
ConclusionesBajo exposición a TW, sacubitrilo/valsartán se asoció con menores incrementos tempranos de Cr en comparación con valsartán, mientras que la intensidad del tratamiento diurético emergió como un determinante consistente del deterioro renal. Aunque no puede establecerse causalidad, estos hallazgos destacan la importancia del manejo del volumen y respaldan la necesidad de estudios prospectivos.
The combined use of RAAS inhibitors and diuretics is a cornerstone of pharmacologic therapy for heart failure. In routine clinical practice, however, NSAIDs are frequently prescribed, often by other specialties. As a result, all three drug classes are sometimes administered concurrently, leading to the so-called “triple whammy.” This combination is associated with an increased risk of renal hemodynamic compromise. Mechanistically, TW represents the convergence of efferent arteriolar dilation caused by RAAS inhibitors, reductions in circulating plasma volume due to diuretics, and afferent arteriolar constriction induced by NSAIDs. Acting together, these effects substantially reduce intraglomerular pressure and the glomerular filtration rate (GFR), thereby predisposing patients to prerenal AKI and other forms of renal dysfunction.1–3
Epidemiologic data highlight the clinical relevance of this interaction. Lapi et al. reported that triple therapy increased the 30-day risk of AKI by 1.82-fold (95% CI, 1.35–2.46) compared with dual therapy consisting of a RAAS inhibitor plus a diuretic.4 In addition, a large population-based study from the United Kingdom showed that 8.8% of adults aged 65 years or older received at least one annual NSAID prescription while concurrently using renin–angiotensin system inhibitors and diuretics.5 These findings underscore the need for clinicians and patients to remain aware of the substantial renal hazards associated with NSAID exposure under these conditions. The 2018 Japanese chronic kidney disease (CKD) guidelines similarly recommend avoiding this triple therapy, particularly in older adults and patients with CKD stage G3b or more advanced disease.6 TW-related renal injury has therefore become an increasingly recognized clinical problem, especially among vulnerable populations such as older adults and individuals with heart failure, dehydration, or multiple comorbidities.1,7
Sacubitril/valsartan, an angiotensin receptor–neprilysin inhibitor (ARNI), has recently been introduced into clinical practice and has demonstrated not only superior outcome benefits in heart failure compared with conventional RAAS inhibitors, but also potential renal safety advantages and renoprotective effects.8,9 Meta-analyses involving heart failure patients with CKD have reported that sacubitril/valsartan may attenuate increases in serum creatinine, slow declines in eGFR, and reduce the progression to end-stage renal disease (ESRD).10–12 Real-world studies also suggest that ARNI therapy may maintain or even improve GFR following initiation.13
Despite these accumulating data, a critical knowledge gap remains. No previous studies have examined whether ARNI therapy confers renal benefit specifically under the high-risk pharmacologic conditions of TW, in which NSAIDs are added to RAAS inhibitors (or ARNI) and diuretics. Consequently, it is unclear whether substituting ARNI for a conventional ARB might reduce or prevent renal impairment induced by TW.
To address this gap, the present study compared renal function trajectories and AKI incidence over 30 days following initiation of NSAID therapy in the setting of concomitant RAAS inhibitor and diuretic use between patients treated with conventional ARB therapy (valsartan) and those treated with ARNI (sacubitril/valsartan). Our objective was to compare renal function changes and AKI incidence following TW exposure between patients receiving valsartan and those receiving sacubitril/valsartan, and to evaluate whether ARNI therapy is associated with differential renal effects under these high-risk conditions.
MethodsStudy design and cohort constructionThis was a single-center retrospective observational study conducted at our institution between May 2013 and July 2024. Adult patients (≥18 years) with heart failure were identified using electronic medical records. Heart failure was defined based on a documented clinical diagnosis registered and confirmed by the attending physician. Eligible patients were required to be receiving stable RAAS inhibitor (either valsartan or sacubitril/valsartan) and diuretic therapy for at least 30 days prior to NSAID initiation, without discontinuation during this period. TW exposure was operationally defined as the new initiation of regularly scheduled oral NSAID therapy in patients already receiving both a RAAS inhibitor and a diuretic. NSAID prescriptions written on an as-needed basis were excluded. A new NSAID prescription was defined as initiation after at least 30 days without any NSAID prescription (washout period). Patients with any NSAID prescription during the preceding 30 days were excluded. The index date was defined as the date of NSAID initiation. The observation period was defined as the 30 days following the index date. Patients were categorized according to the type of RAAS inhibitor used at the time of NSAID initiation into the valsartan group or the sacubitril/valsartan group.
Exclusion criteriaPatients were excluded if they (1) had AKI at the time of NSAID initiation, (2) were receiving maintenance dialysis, or (3) did not have SCr measured on the index date, (4) lacked follow-up renal laboratory data within 30 days after NSAID initiation. Baseline SCr was defined as the value measured on the day of NSAID initiation.
Data collection and clinical variablesDemographic and clinical variables were extracted from electronic medical records. Data on heart failure severity, including plasma B-type natriuretic peptide (BNP) levels and left ventricular ejection fraction (LVEF), were obtained from the most recent available records prior to NSAID initiation. Because BNP and LVEF were not routinely measured at the exact time of NSAID initiation, the most recent values recorded during the preceding clinical follow-up period while patients were receiving RAAS inhibitor and diuretic therapy were used for analysis. Post-initiation BNP and LVEF data were incomplete in some patients and were not included in outcome analyses.
Baseline diuretic exposure was assessed using furosemide-equivalent doses. Loop diuretic doses were converted to furosemide-equivalent doses using standard conversion ratios (furosemide 40mg=torasemide 20mg=azosemide 60mg=bumetanide 1mg). Non-loop diuretics were analyzed separately and were not converted to loop-equivalent doses.
Definition of renal outcomesAKI was defined according to the Kidney Disease: Improving Global Outcomes (KDIGO) criteria,14 based solely on serum creatinine changes, specifically: an increase in SCr of ≥0.3mg/dL within 30 days after NSAID initiation. Urine output criteria were not applied because reliable urine volume data were not consistently available in this retrospective cohort. For each patient, the highest SCr value measured within the 30-day observation window was used to determine the presence or absence of AKI. The relative change in SCr was calculated as: ln(peak SCr/baseline SCr).
Statistical analysisThe Shapiro–Wilk test was used to evaluate the normality of continuous variables. Between-group comparisons were performed as follows: continuous variables were compared using Welch's t-test or the Mann–Whitney U test for unpaired analyses, and paired t-tests or Wilcoxon signed-rank tests for paired analyses. Categorical variables were compared using Fisher's exact test. To identify independent determinants of SCr change, multiple linear regression analysis was performed with the relative change in SCr as the dependent variable. To evaluate factors associated with AKI (SCr increase ≥0.3mg/dL), multivariable logistic regression analysis was performed. Because of the limited number of AKI events, logistic regression was conducted using Firth's penalized likelihood method to reduce small-sample bias, address sparse event counts, and minimize the risk of model instability or separation. Variables included in the multivariable logistic regression model were selected a priori based on clinical relevance and prior literature identifying established risk factors for acute kidney injury, including age, baseline renal function, loop diuretic dose, and the exposure of interest (sacubitril/valsartan use), rather than statistical significance alone.15,16 Results of linear regression are presented as regression coefficients (B) with 95% confidence intervals (CI). Logistic regression results are presented as odds ratios (OR) with 95% CI. All statistical analyses were performed using BellCurve for Excel (Social Survey Research Information Co., Ltd., Tokyo, Japan), except for Firth's penalized logistic regression, which was conducted using R software (version 4.5.1; R Foundation for Statistical Computing, Vienna, Austria). A two-tailed P value <0.05 was considered statistically significant.
Ethical considerationsThis study was conducted in accordance with institutional and national research ethics guidelines, as well as the principles of the Declaration of Helsinki (1964) and its later revisions. The study protocol was approved by an institutional review board (Approval No. 36-022 [12121]). Informed consent for participation and use of clinical data was obtained through an opt-out process.
ResultsStudy population and baseline characteristicsDuring the study period, 168 patients met the eligibility criteria and were included in the analysis: 71 patients in the valsartan group and 97 patients in the sacubitril/valsartan group, classified according to the RAAS inhibitor administered at the time of NSAID initiation (index date).
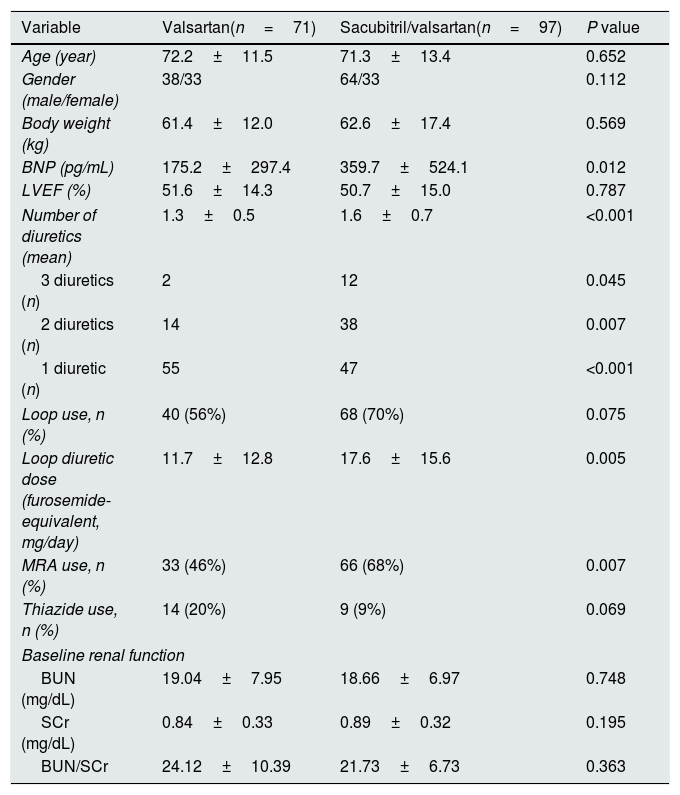
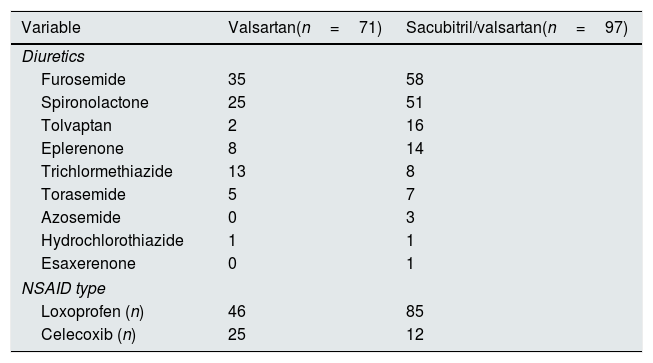
Baseline clinical characteristics are summarized in Table 1. Loop diuretic dose (furosemide-equivalent) was higher in the sacubitril/valsartan group (17.6±15.6mg/day) than in the valsartan group (11.7±12.8mg/day), although the difference did not reach statistical significance (P=0.005). The distribution of concomitant diuretics and NSAIDs is shown in Table 2. The mean number of diuretics administered was significantly higher in the sacubitril/valsartan group (1.6±0.7) than in the valsartan group (1.3±0.5) (P<0.001). Notably, the proportion of patients receiving three diuretics was significantly greater in the sacubitril/valsartan group, whereas single-diuretic use was significantly more common in the valsartan group. BNP levels, based on the most recent measurements prior to NSAID initiation, were significantly higher in the sacubitril/valsartan group compared with the valsartan group (P=0.012), whereas LVEF did not differ significantly between groups. Baseline serum creatinine values did not differ significantly between groups. The mean duration of NSAID exposure following initiation of triple therapy was 12.8±8.7 days in the valsartan group and 10.9±8.1 days in the sacubitril/valsartan group (P=0.161). Loop diuretic dose and number of concomitant diuretics were both higher in the sacubitril/valsartan group, indicating a greater diuretic burden at baseline.
Baseline characteristics at the time of NSAID initiation.
| Variable | Valsartan(n=71) | Sacubitril/valsartan(n=97) | P value |
|---|---|---|---|
| Age (year) | 72.2±11.5 | 71.3±13.4 | 0.652 |
| Gender (male/female) | 38/33 | 64/33 | 0.112 |
| Body weight (kg) | 61.4±12.0 | 62.6±17.4 | 0.569 |
| BNP (pg/mL) | 175.2±297.4 | 359.7±524.1 | 0.012 |
| LVEF (%) | 51.6±14.3 | 50.7±15.0 | 0.787 |
| Number of diuretics (mean) | 1.3±0.5 | 1.6±0.7 | <0.001 |
| 3 diuretics (n) | 2 | 12 | 0.045 |
| 2 diuretics (n) | 14 | 38 | 0.007 |
| 1 diuretic (n) | 55 | 47 | <0.001 |
| Loop use, n (%) | 40 (56%) | 68 (70%) | 0.075 |
| Loop diuretic dose (furosemide-equivalent, mg/day) | 11.7±12.8 | 17.6±15.6 | 0.005 |
| MRA use, n (%) | 33 (46%) | 66 (68%) | 0.007 |
| Thiazide use, n (%) | 14 (20%) | 9 (9%) | 0.069 |
| Baseline renal function | |||
| BUN (mg/dL) | 19.04±7.95 | 18.66±6.97 | 0.748 |
| SCr (mg/dL) | 0.84±0.33 | 0.89±0.32 | 0.195 |
| BUN/SCr | 24.12±10.39 | 21.73±6.73 | 0.363 |
Mann–Whitney U test or Fisher's exact test as appropriate; BNP, brain natriuretic peptide; LVEF, left ventricular ejection fraction; MRA, mineralocorticoid receptor antagonist; SCr, serum creatinine; BUN, blood urea nitrogen.
Concomitant diuretics at baseline and NSAID type at initiation.
| Variable | Valsartan(n=71) | Sacubitril/valsartan(n=97) |
|---|---|---|
| Diuretics | ||
| Furosemide | 35 | 58 |
| Spironolactone | 25 | 51 |
| Tolvaptan | 2 | 16 |
| Eplerenone | 8 | 14 |
| Trichlormethiazide | 13 | 8 |
| Torasemide | 5 | 7 |
| Azosemide | 0 | 3 |
| Hydrochlorothiazide | 1 | 1 |
| Esaxerenone | 0 | 1 |
| NSAID type | ||
| Loxoprofen (n) | 46 | 85 |
| Celecoxib (n) | 25 | 12 |
NSAIDs, nonsteroidal anti-inflammatory drugs.
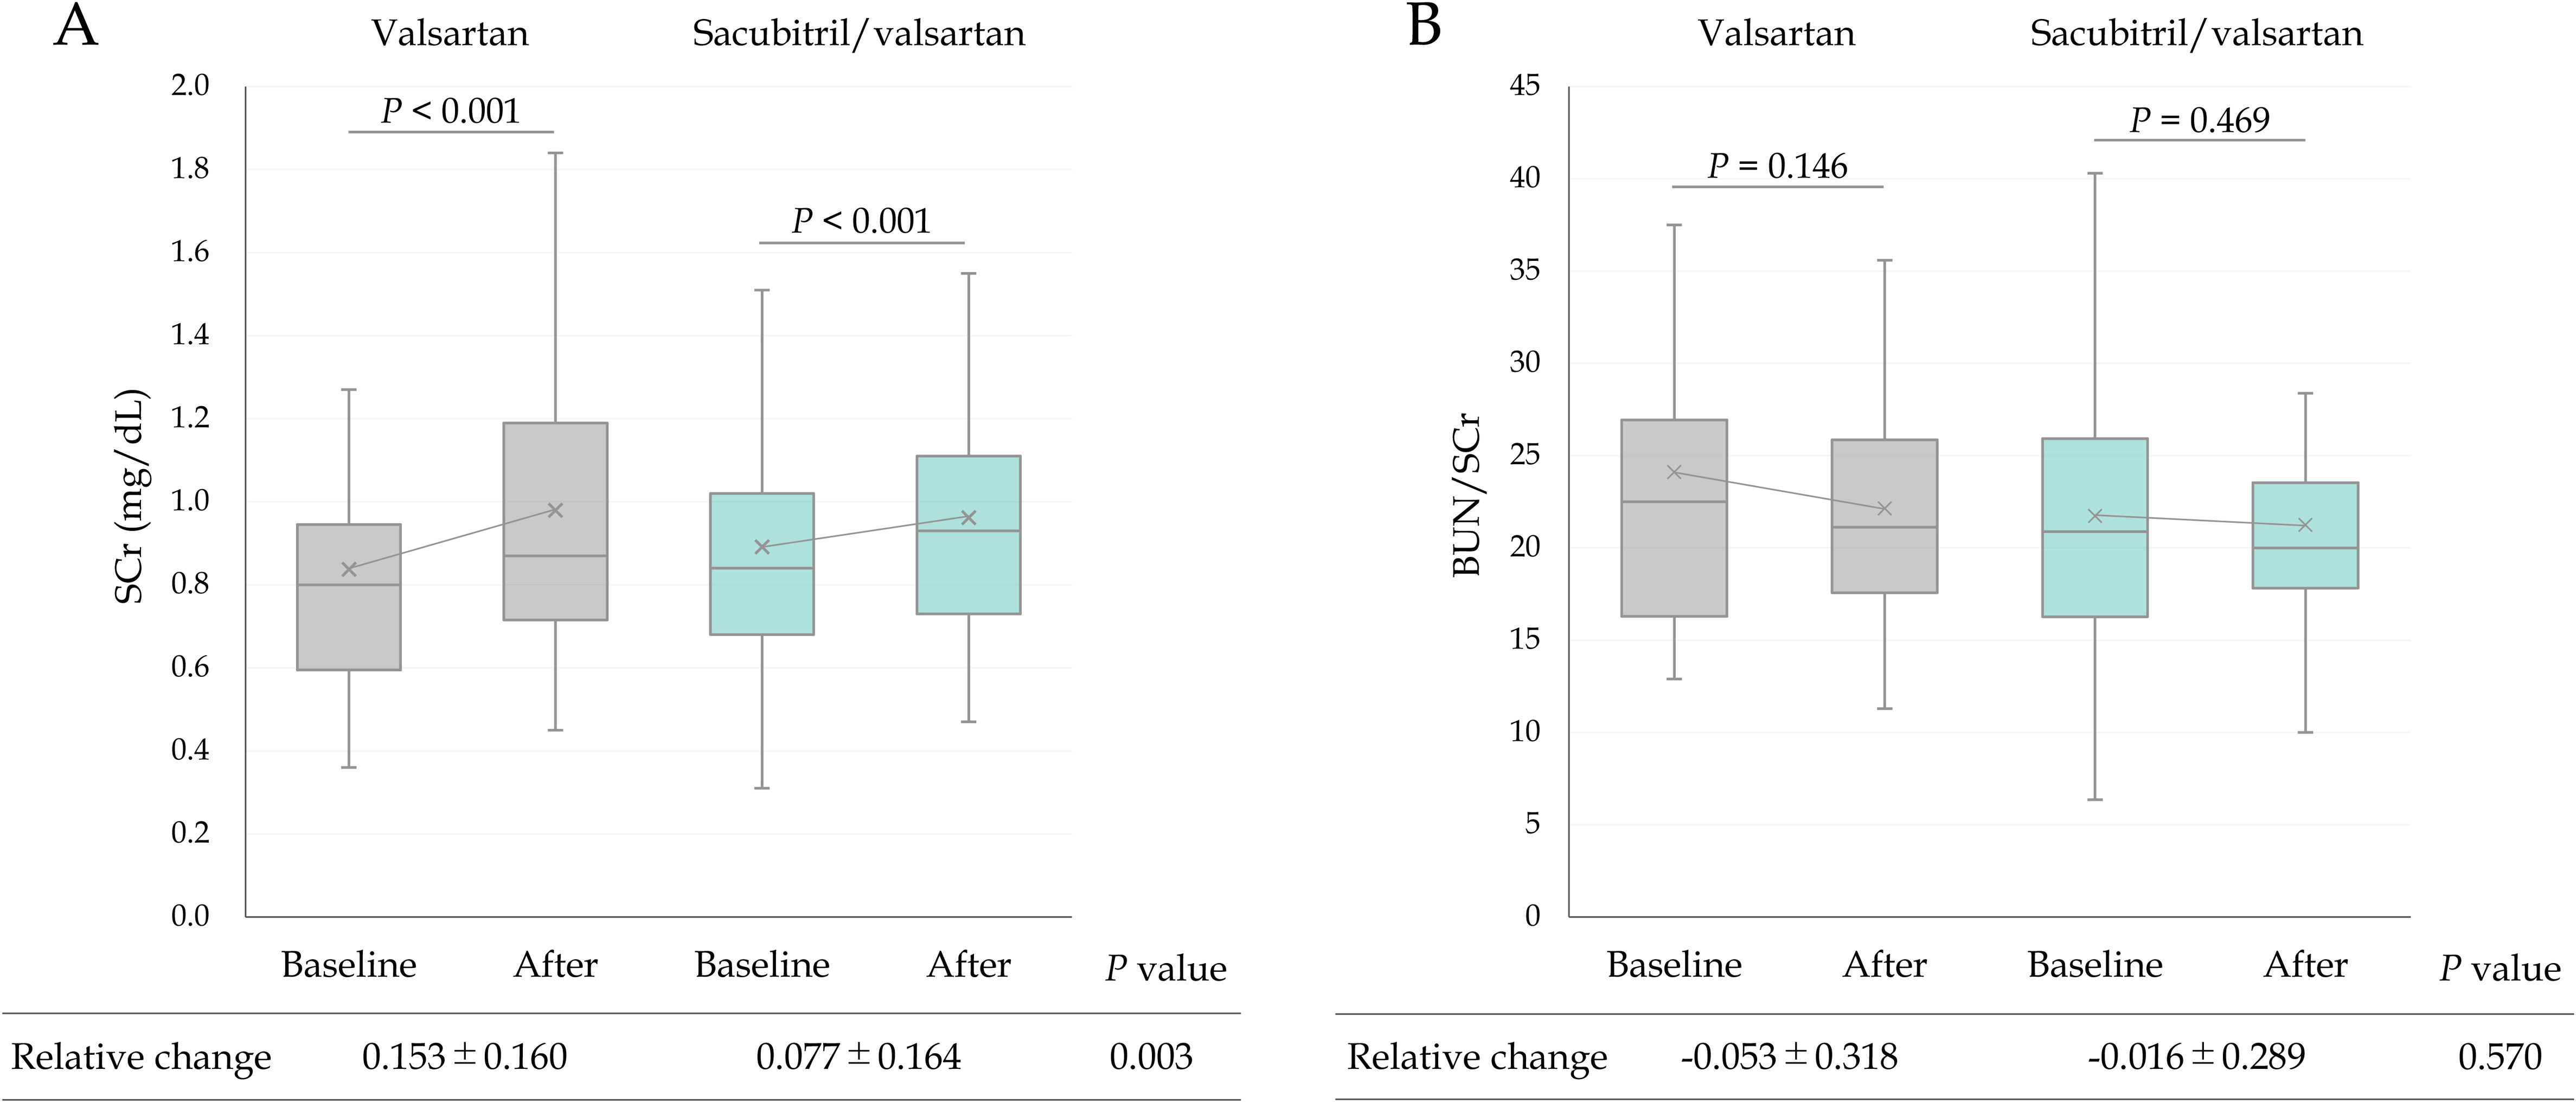
Changes in serum SCr and the BUN/SCr ratio from baseline (index date) to the highest value within the 30-day observation period are shown in Fig. 1. In the valsartan group, mean SCr increased significantly from 0.84±0.33 to 0.98±0.38mg/dL. In the sacubitril/valsartan group, SCr also increased significantly, from 0.89±0.32 to 0.96±0.64mg/dL. The relative change in SCr, calculated as the natural logarithmic difference between peak and baseline values, was significantly greater in the valsartan group than in the sacubitril/valsartan group (0.153±0.160 vs 0.077±0.164, P=0.003). In contrast, no significant changes were observed in the BUN/SCr ratio in either group, and the relative changes did not differ significantly between groups.

Changes in serum creatinine (SCr) (A) and blood urea nitrogen-to-creatinine ratio (BUN/SCr) (B) following initiation of triple therapy. Triple therapy was defined as concomitant use of a renin–angiotensin system inhibitor, a diuretic, and a nonsteroidal anti-inflammatory drug. Values represent mean±standard deviation at baseline and peak levels within 30 days. Between-group comparisons of relative change were performed using Welch's t-test. Abbreviations: SCr, serum creatinine; BUN, blood urea nitrogen.
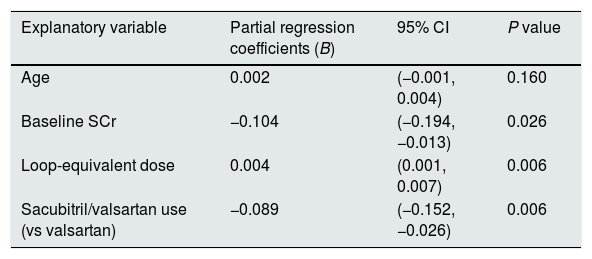
Multiple linear regression analysis was performed to identify factors independently associated with the relative change in SCr. Explanatory variables included age, baseline serum creatinine, loop diuretic dose (furosemide-equivalent), and use of sacubitril/valsartan (reference: valsartan). As shown in Table 3, higher loop-equivalent dose was associated with greater SCr elevation (P=0.006), whereas sacubitril/valsartan use was associated with a smaller increase compared with valsartan (P=0.006). Baseline SCr showed an inverse association with relative change (P=0.026), while age was not significant.
Multiple linear regression analysis for factors associated with changes in serum creatinine.
| Explanatory variable | Partial regression coefficients (B) | 95% CI | P value |
|---|---|---|---|
| Age | 0.002 | (−0.001, 0.004) | 0.160 |
| Baseline SCr | −0.104 | (−0.194, −0.013) | 0.026 |
| Loop-equivalent dose | 0.004 | (0.001, 0.007) | 0.006 |
| Sacubitril/valsartan use (vs valsartan) | −0.089 | (−0.152, −0.026) | 0.006 |
R2=0.167; SCr, serum creatinine; CI, confidence interval.
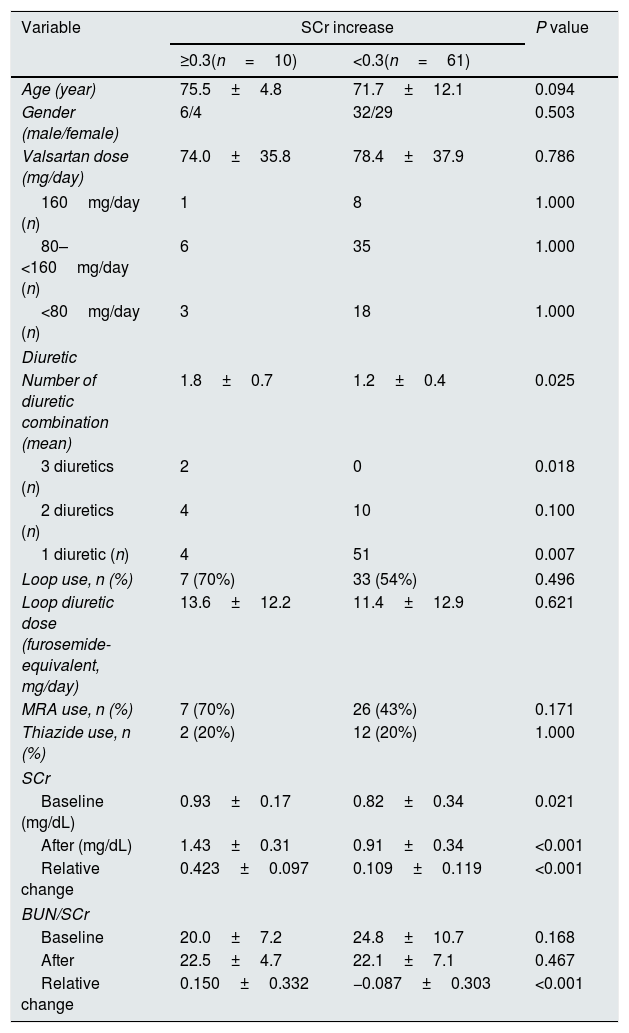
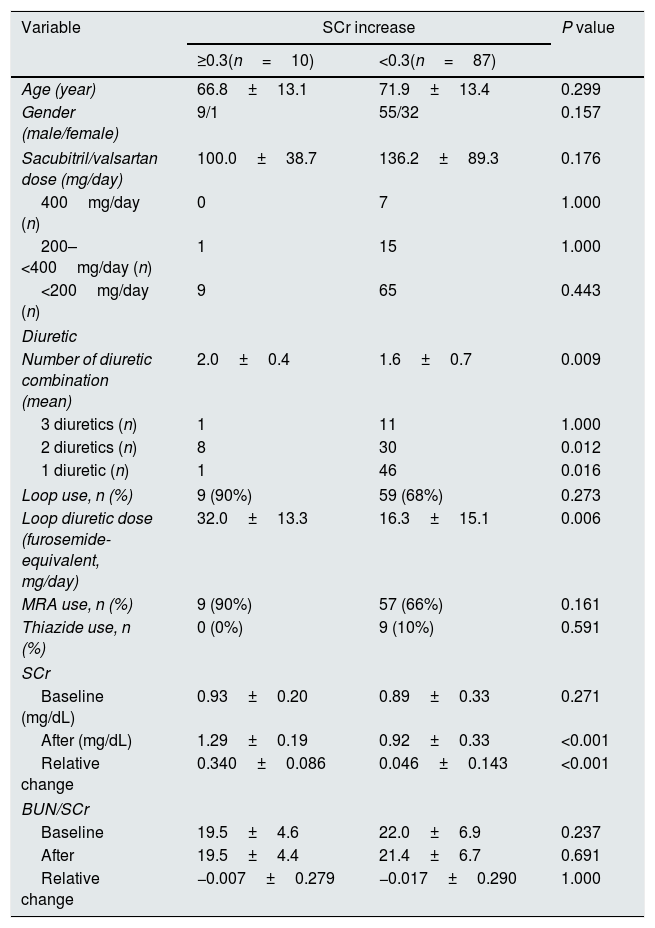
Within the valsartan group, patients who developed AKI had significantly higher baseline SCr (0.93±0.17 vs 0.82±0.34mg/dL), a greater number of concomitant diuretics (1.8±0.7 vs 1.2±0.4) compared with those without AKI (Table 4). Loop diuretic use and loop-equivalent dose were numerically higher in patients with AKI, although these differences did not reach statistical significance. Within the sacubitril/valsartan group, patients who developed AKI received a significantly greater number of concomitant diuretics (2.0±0.4 vs 1.6±0.7) and a significantly higher loop-equivalent diuretic dose (32.0±13.3 vs 16.3±15.1mg/day) compared with those without AKI (Table 5). Baseline SCr and other baseline characteristics did not differ significantly between groups.
Patient characteristics according to SCr increase (≥0.3 vs <0.3mg/dL) in the valsartan group.
| Variable | SCr increase | P value | |
|---|---|---|---|
| ≥0.3(n=10) | <0.3(n=61) | ||
| Age (year) | 75.5±4.8 | 71.7±12.1 | 0.094 |
| Gender (male/female) | 6/4 | 32/29 | 0.503 |
| Valsartan dose (mg/day) | 74.0±35.8 | 78.4±37.9 | 0.786 |
| 160mg/day (n) | 1 | 8 | 1.000 |
| 80–<160mg/day (n) | 6 | 35 | 1.000 |
| <80mg/day (n) | 3 | 18 | 1.000 |
| Diuretic | |||
| Number of diuretic combination (mean) | 1.8±0.7 | 1.2±0.4 | 0.025 |
| 3 diuretics (n) | 2 | 0 | 0.018 |
| 2 diuretics (n) | 4 | 10 | 0.100 |
| 1 diuretic (n) | 4 | 51 | 0.007 |
| Loop use, n (%) | 7 (70%) | 33 (54%) | 0.496 |
| Loop diuretic dose (furosemide-equivalent, mg/day) | 13.6±12.2 | 11.4±12.9 | 0.621 |
| MRA use, n (%) | 7 (70%) | 26 (43%) | 0.171 |
| Thiazide use, n (%) | 2 (20%) | 12 (20%) | 1.000 |
| SCr | |||
| Baseline (mg/dL) | 0.93±0.17 | 0.82±0.34 | 0.021 |
| After (mg/dL) | 1.43±0.31 | 0.91±0.34 | <0.001 |
| Relative change | 0.423±0.097 | 0.109±0.119 | <0.001 |
| BUN/SCr | |||
| Baseline | 20.0±7.2 | 24.8±10.7 | 0.168 |
| After | 22.5±4.7 | 22.1±7.1 | 0.467 |
| Relative change | 0.150±0.332 | −0.087±0.303 | <0.001 |
Mann–Whitney U test or Fisher's exact test as appropriate; MRA, mineralocorticoid receptor antagonist; SCr, serum creatinine; BUN, blood urea nitrogen.
Patient characteristics according to SCr increase (≥0.3 vs <0.3mg/dL) in the sacubitril/valsartan group.
| Variable | SCr increase | P value | |
|---|---|---|---|
| ≥0.3(n=10) | <0.3(n=87) | ||
| Age (year) | 66.8±13.1 | 71.9±13.4 | 0.299 |
| Gender (male/female) | 9/1 | 55/32 | 0.157 |
| Sacubitril/valsartan dose (mg/day) | 100.0±38.7 | 136.2±89.3 | 0.176 |
| 400mg/day (n) | 0 | 7 | 1.000 |
| 200–<400mg/day (n) | 1 | 15 | 1.000 |
| <200mg/day (n) | 9 | 65 | 0.443 |
| Diuretic | |||
| Number of diuretic combination (mean) | 2.0±0.4 | 1.6±0.7 | 0.009 |
| 3 diuretics (n) | 1 | 11 | 1.000 |
| 2 diuretics (n) | 8 | 30 | 0.012 |
| 1 diuretic (n) | 1 | 46 | 0.016 |
| Loop use, n (%) | 9 (90%) | 59 (68%) | 0.273 |
| Loop diuretic dose (furosemide-equivalent, mg/day) | 32.0±13.3 | 16.3±15.1 | 0.006 |
| MRA use, n (%) | 9 (90%) | 57 (66%) | 0.161 |
| Thiazide use, n (%) | 0 (0%) | 9 (10%) | 0.591 |
| SCr | |||
| Baseline (mg/dL) | 0.93±0.20 | 0.89±0.33 | 0.271 |
| After (mg/dL) | 1.29±0.19 | 0.92±0.33 | <0.001 |
| Relative change | 0.340±0.086 | 0.046±0.143 | <0.001 |
| BUN/SCr | |||
| Baseline | 19.5±4.6 | 22.0±6.9 | 0.237 |
| After | 19.5±4.4 | 21.4±6.7 | 0.691 |
| Relative change | −0.007±0.279 | −0.017±0.290 | 1.000 |
Mann–Whitney U test or Fisher's exact test as appropriate; MRA, mineralocorticoid receptor antagonist; SCr, serum creatinine; BUN, blood urea nitrogen.
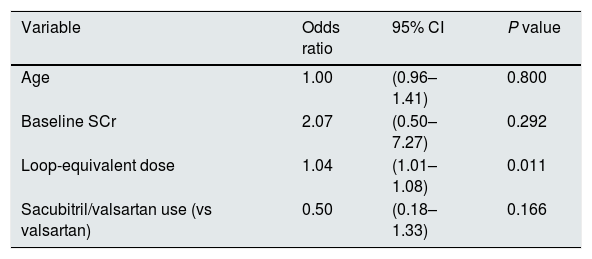
To identify independent predictors of AKI, Firth's penalized logistic regression analysis was performed due to the limited number of events and the potential risk of model instability. Higher loop-equivalent diuretic dose was significantly associated with AKI, whereas age, baseline SCr, and sacubitril/valsartan use were not independently associated with AKI (Table 6).
Univariate Firth logistic regression analysis of factors associated with an increase in SCr ≥0.3mg/dL.
| Variable | Odds ratio | 95% CI | P value |
|---|---|---|---|
| Age | 1.00 | (0.96–1.41) | 0.800 |
| Baseline SCr | 2.07 | (0.50–7.27) | 0.292 |
| Loop-equivalent dose | 1.04 | (1.01–1.08) | 0.011 |
| Sacubitril/valsartan use (vs valsartan) | 0.50 | (0.18–1.33) | 0.166 |
Estimates were obtained using Firth's penalized likelihood method; SCr, serum creatinine; CI, confidence interval.
This study investigated the renal effects of sacubitril/valsartan compared with valsartan in patients exposed to the high-risk combination of RAAS inhibition, diuretics, and NSAIDs, which is commonly known as the TW. This represents a novel and clinically relevant perspective because prior research has largely compared RAAS inhibitors in isolation,17 with limited evaluation of real-world prescribing patterns that frequently involve NSAIDs and multiple diuretics. In this retrospective observational study of patients receiving RAAS inhibitors and diuretics who initiated NSAID therapy, sacubitril/valsartan use was associated with smaller relative increases in serum creatinine compared with valsartan. In contrast, higher loop-equivalent diuretic dose was independently associated with greater renal function deterioration. These findings suggest that under triple-drug exposure, diuretic intensity may be a primary determinant of acute renal vulnerability, while the type of RAAS inhibition may modulate early creatinine dynamics.
Prior clinical evidence supports a favorable renal profile of sacubitril/valsartan.13,18,19 However, its renal effects under triple-drug exposure involving NSAIDs, RAAS inhibition, and diuretics remain unclear. Therefore, the present study addresses an important gap in the literature. Although prior randomized trials and meta-analyses have demonstrated a favorable renal profile of sacubitril/valsartan compared with conventional RAAS inhibitors in heart failure populations, these studies did not specifically evaluate patients concurrently exposed to NSAIDs and substantial diuretic burden.10 Given that temporary NSAID use is common in clinical practice, particularly among patients with cardiovascular comorbidities, our analysis provides real-world insight into renal responses under this clinically relevant pharmacologic stress.
Notably, patients receiving sacubitril/valsartan had higher baseline BNP levels and were treated with a greater number of concomitant diuretics, suggesting more advanced heart failure severity. Despite this potentially higher-risk profile, relative increases in serum creatinine were attenuated in this group. Although residual confounding and confounding by indication cannot be excluded, these observations suggest that differences in baseline risk alone are unlikely to fully explain the observed renal findings.
In multivariable analyses, higher loop-equivalent diuretic dose was independently associated with AKI defined by a ≥0.3mg/dL increase in serum creatinine. Sacubitril/valsartan use, however, was not independently associated with overt AKI. The dissociation between smaller relative creatinine changes and unchanged AKI incidence suggests that sacubitril/valsartan may attenuate early or mild renal functional fluctuations without substantially altering the risk of clinically defined AKI. This distinction highlights the importance of evaluating continuous renal function changes in addition to dichotomous AKI endpoints, particularly in studies with limited event numbers. Consistent with these findings, subgroup analyses within the sacubitril/valsartan group demonstrated that loop-equivalent diuretic dose was significantly higher among patients who developed AKI compared with those who did not. This concordance between subgroup comparisons and multivariable Firth logistic regression further supports the central role of diuretic intensity as a key determinant of renal vulnerability under triple-drug exposure.
Several mechanisms may account for these findings. Neprilysin inhibition augments natriuretic peptide activity, promoting vasodilation and natriuresis, which may help preserve renal perfusion in the setting of NSAID-induced afferent arteriolar constriction and diuretic-related effective volume depletion. Improved systemic hemodynamics in heart failure may further contribute to renal perfusion stability. However, these mechanistic interpretations remain speculative and require confirmation in prospective physiological studies.
From a clinical perspective, our results emphasize careful diuretic management when NSAIDs are initiated in patients receiving RAAS inhibition. While our data do not support definitive renoprotective claims for sacubitril/valsartan in this context, they generate the hypothesis that RAAS inhibitor selection may influence early renal responses under pharmacologic stress.
Several limitations should be considered. First, this was a retrospective observational study, and residual confounding cannot be excluded. Second, NSAID exposure was defined based on prescription data; actual adherence and precise dosing could not be verified, potentially resulting in exposure misclassification and limiting assessment of dose–response relationships. Third, AKI was defined solely based on changes in serum creatinine because reliable urine output data were unavailable, which may have led to misclassification of events. Fourth, markers of heart failure severity such as BNP and LVEF were not uniformly available at the time of NSAID initiation, and due to their incomplete availability and the risk of overfitting given the limited number of events, these variables were not included in the multivariable models. Finally, loxoprofen was the predominant NSAID in this cohort, reflecting regional prescribing patterns in Japan; therefore, generalizability to other populations with different NSAID utilization patterns may be limited. Larger prospective studies with greater event numbers and standardized assessment of heart failure severity and NSAID exposure are warranted to confirm these findings.
ConclusionIn patients exposed to concurrent RAAS inhibition, diuretics, and NSAIDs, sacubitril/valsartan was associated with smaller early increases in serum creatinine compared with valsartan, whereas diuretic intensity emerged as a consistent determinant of renal deterioration. These findings underscore the central role of volume management under triple-drug exposure. Although causality cannot be established, the results support prospective studies to clarify differential renal hemodynamic responses among RAAS inhibitors.
CRediT authorship contribution statementYN conceived and designed the study and drafted the manuscript; MN collected the data and performed the statistical analysis; YK contributed to the study design and provided clinical interpretation of the data; TK critically revised the manuscript for important intellectual content and gave final approval of the version to be published.
Ethical approvalThis study was conducted in accordance with the Declaration of Helsinki and was approved by the Institutional Review Board of The Jikei University School of Medicine (Approval No. 36-022 [12121]).
Informed consentThe requirement for written informed consent was waived because of the retrospective study design, and an opt-out consent process was applied.
Declaration of generative AI and AI-assisted technologies in the writing processThe authors used ChatGPT (OpenAI) for language editing and polishing of the manuscript. The authors reviewed and revised the content and take full responsibility for the integrity of the work.
FundingThis research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
Conflict of interestThe authors declare no conflicts of interest.
Data availabilityThe data that support the findings of this study are available from the corresponding author upon reasonable request.




