



Infectious complications of peritoneal dialysis (PD) remain a major threat to technique survival, despite advances in preventive strategies.1,2 Standard PD catheters incorporate double polyester cuffs. The external cuff anchors the catheter in the subcutaneous tissue and acts as a barrier to infection. Exit-site infection (ESI) is defined as purulent discharge with/without surrounding erythema, while tunnel infection (TI) is characterized by inflammatory signs along the catheter tunnel, with/without ultrasonographic evidence of fluid collection.3 TI may be further classified as superficial or deep according to cuff involvement.4
Current recommendations suggest oral antibiotic therapy for at least two weeks in ESI and prolonged therapy in TI.3 Deep TI, with cuff involvement, is frequently refractory to medical therapy and may require catheter removal in about 40% of cases. Refractory infections are associated with an increased risk of peritonitis, catheter loss, treatment interruption, and higher healthcare burden.5
To avoid infection-related catheter removal, salvage strategies such as external cuff shaving, partial reimplantation, and exit-site relocation have been proposed.6–8 However, evidence supporting these approaches remains limited, and no standardized recommendations exist regarding optimal timing or patient selection. Ultrasound (US) may assist in identifying tunnel involvement, but its role in guiding management decisions has not been clearly established.9,10
We report our single-center experience with external cuff shaving as a strategy for refractory catheter-related infections (failure to respond after 2 weeks of effective antibiotic therapy and appropriately exit site care, or 3 weeks if due to Pseudomonas specie). We also propose a pragmatic management approach based on clinical practice and expert opinion.
We retrospectively reviewed all external cuff shaving procedures performed in our PD unit between January 2019 and February 2025. Catheter preservation was defined as continued use of the original catheter without removal during follow-up.
Initially, cuff shaving was performed by nephrologists in the outpatient setting. Following institutional reorganization and reduced availability of nephrologists experienced in this technique, the procedure was transferred to the General Surgery department and is currently performed in a peripheral operating room. The intervention is carried out under local anesthesia with standard skin disinfection. A small incision is made along the catheter tunnel, followed by subcutaneous dissection to remove the external cuff using electrocautery. The skin is then closed at this point with adhesive strips. Patients are followed in the outpatient clinic two times a week for dressing changes until complete wound healing, for at least one month.
Sixteen external cuff shaving procedures were performed in 15 patients, all with active ESI and/or TI. One patient required a second procedure because the initial attempt was interrupted due to an acute drug-related allergic reaction, resulting in incomplete cuff removal. Of the total, 53% patients were male with a mean age of 48.8±15.2 years. The mean time on PD was 1.6±1.3 years. Approximately two-thirds of patients had experienced a non-peritoneal dialysis related infection within the preceding six months. The most frequent etiology of chronic kidney disease (in 40%) was IgA nephropathy.
Pseudomonas aeruginosa was the predominant pathogen, accounting for nearly half of the isolates (n=7; 43.8%). Other Gram-negative organisms included Serratia marcescens (n=3). Gram-positive pathogens were less frequent and comprised Staphylococcus aureus (n=2), Streptococcus agalactiae, Corynebacterium species and Actinomyces meyeri (n=1, for each).
Ultrasound was performed in four patients and identified pericatheter fluid collections in two (of 1.8 and 2.3mm) and hypoechoic area in one. Although US was not used systematically, it led to earlier intervention in these patients.
No procedure-related complications were observed. Catheter preservation was achieved in 12 cases (75%). In these patients, the median interval between initial positive culture and cuff shaving was 41 (IQR 51.5) days. This interval was shorter in the four patients that underwent US evaluation (36 days; IQR 13.8). Catheter removal was required in three patients due to persistent (n=2) or recurrent infection (n=1), despite cuff shaving and appropriate antibiotic therapy. In these patients, median interval between positive culture and cuff shaving was 65.5 (IQR 74.5) days.
In this single-center experience, external cuff shaving was a feasible salvage option in selected patients with refractory catheter-related infections, allowing catheter preservation in most cases, without procedure-related complications. However, the retrospective design, small sample size, and heterogeneity in management limit the generalizability of these findings.
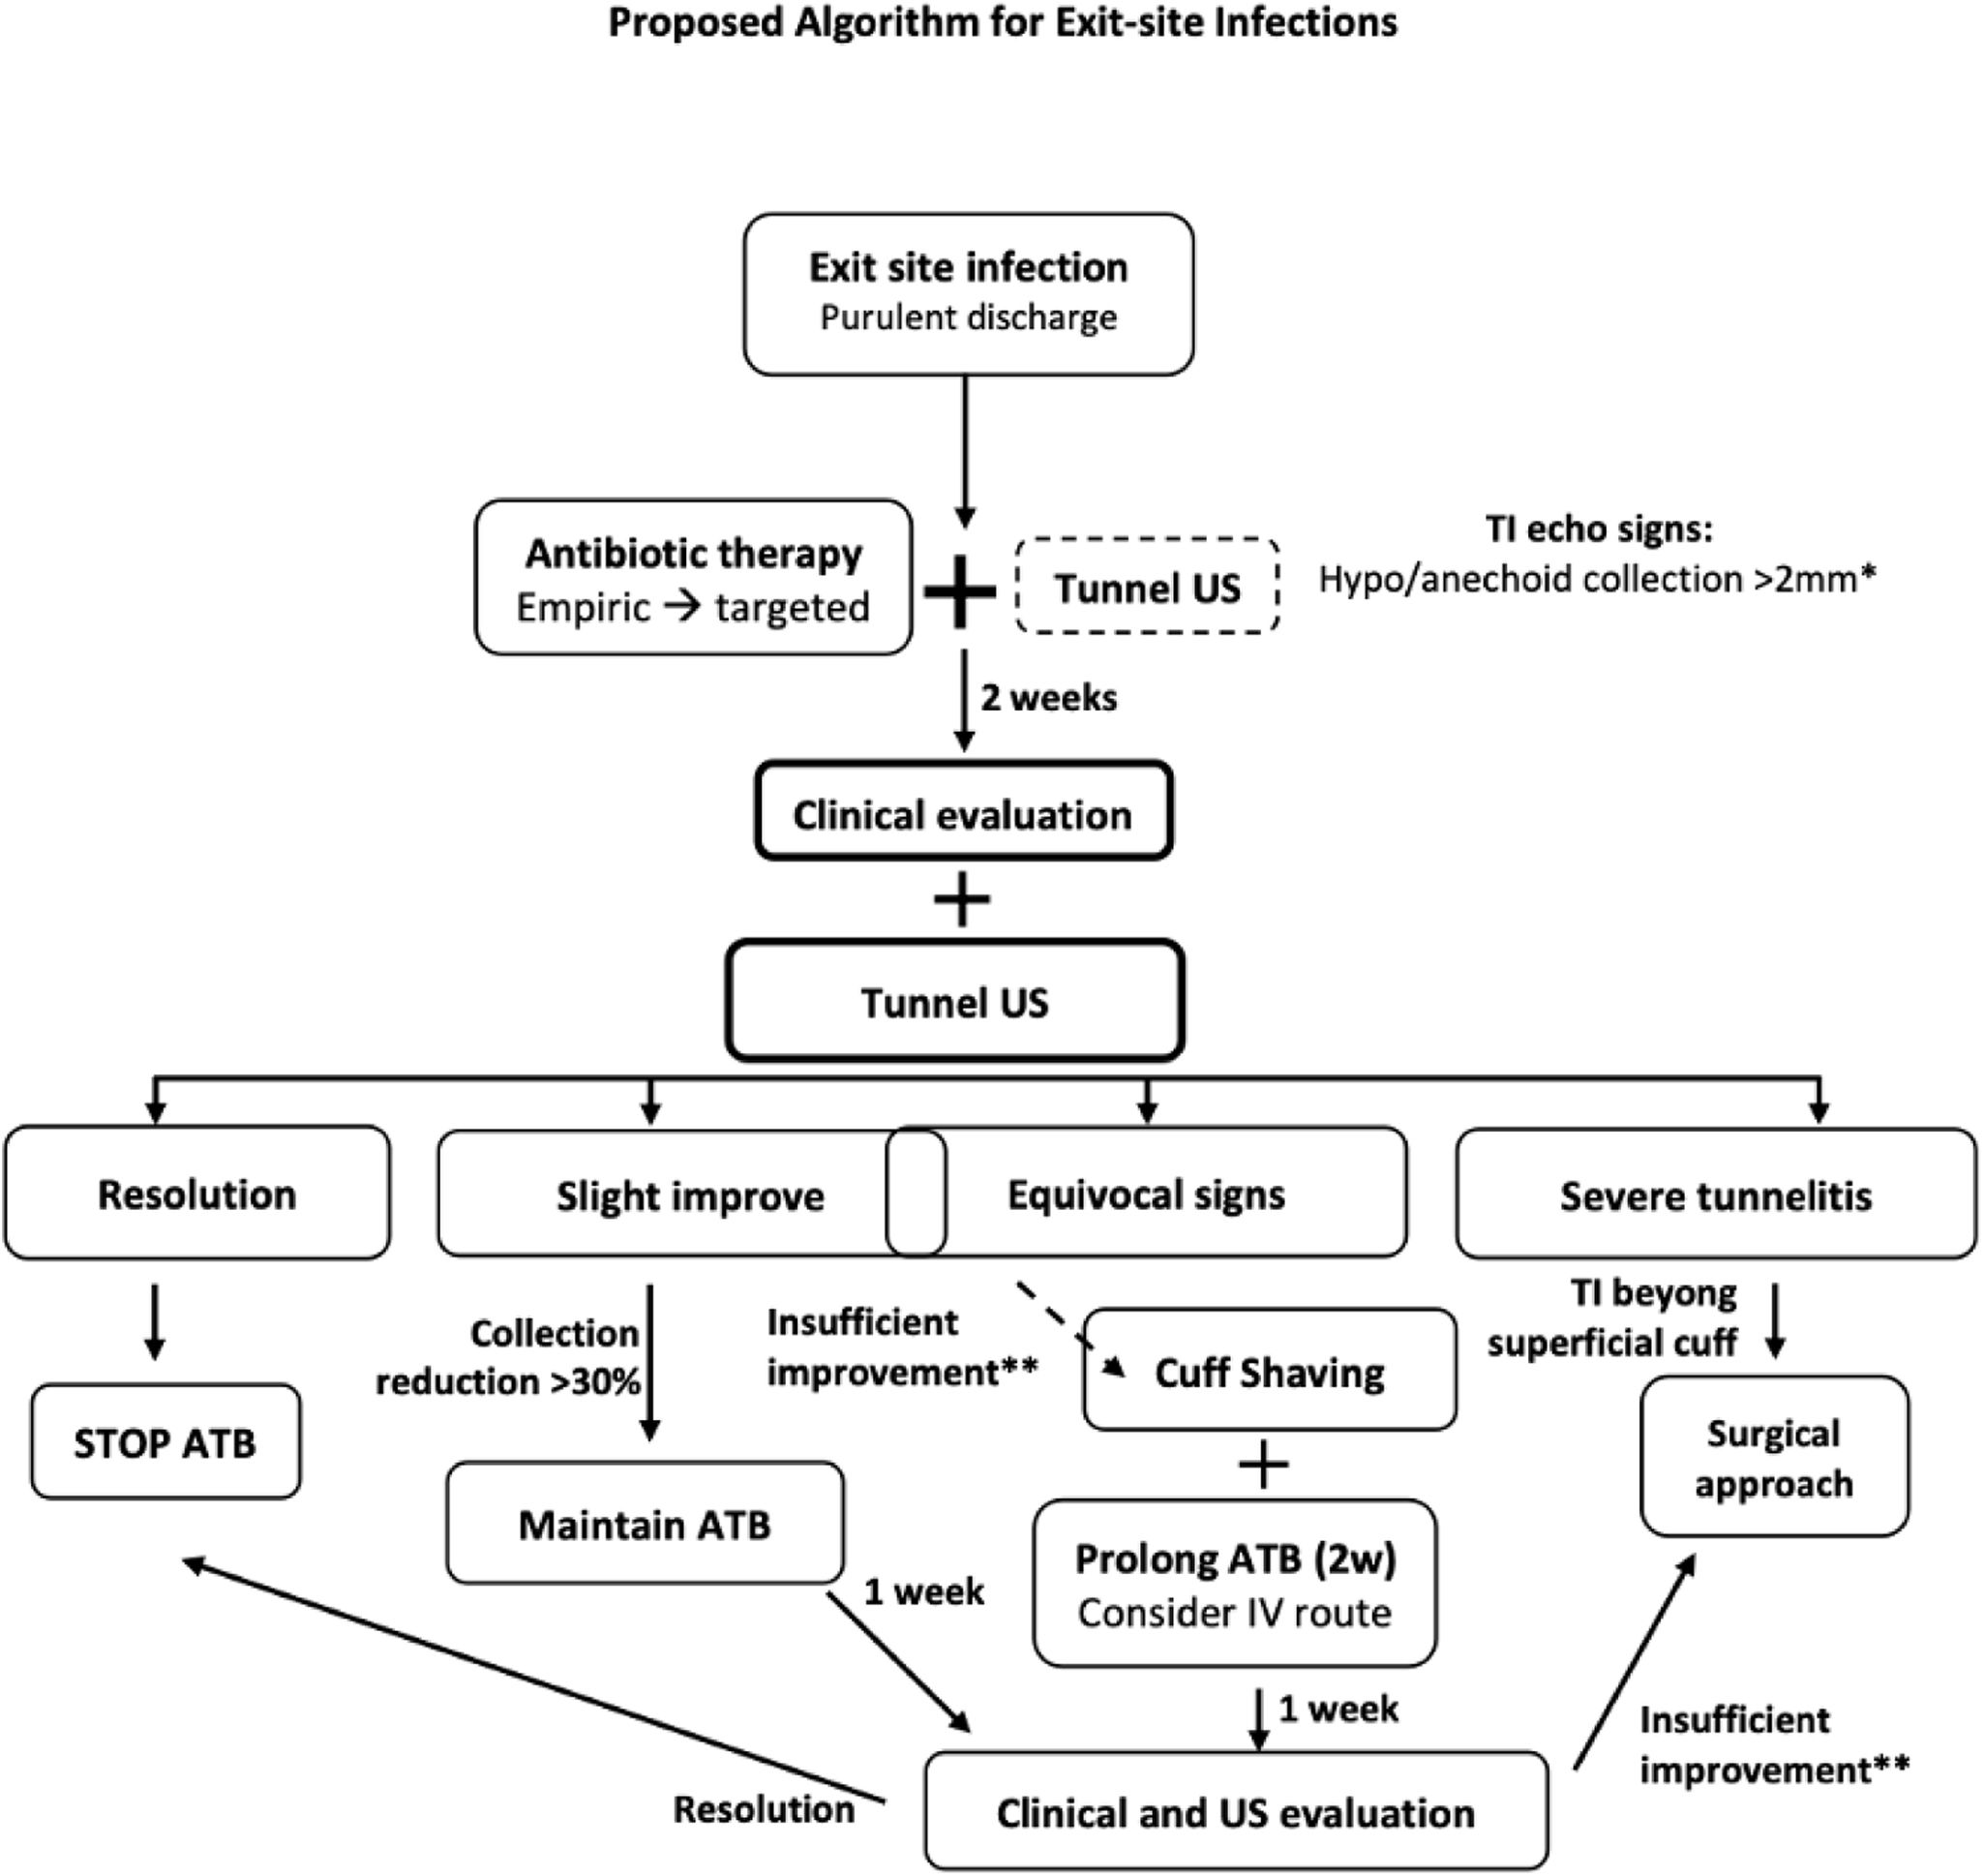
US was not systematically used throughout the study, and therefore its impact on outcomes cannot be formally assessed. Nevertheless, in selected cases, ultrasonographic findings were considered helpful in identifying tunnel involvement and supporting anticipated decision-making. The proposed management algorithm presented in Fig. 1 should be interpreted as a pragmatic approach based on institutional experience and expert opinion, rather than a recommendation derived directly from the study data.

Proposed management approach for exit-site infections in peritoneal dialysis based on expert opinion. TI: tunnel infection; US: ultrasonography; ATB: antibiotic; IV: intravenous; w: weeks. *2mm: distance between the catheter wall and the surrounding tissues. **Improvement: collection reduction <30%; worsening signs of infection.
Prospective studies with standardized diagnostic criteria and management protocols are needed to better define the optimal timing of cuff shaving and to clarify the role of ultrasound in therapeutic decisions.
Conflicts of interestNone declared.




