




Anti-glomerular basement membrane disease (anti-GBM) is a rare autoimmune disorder characterized by autoantibodies targeting antigens in the glomerular and alveolar basement membranes, often leading to rapidly progressive glomerulonephritis and pulmonary hemorrhage. Contemporary real-world data on clinical presentation and long-term renal outcomes remain scarce. This study aims to examine the clinical and pathological features, as well as renal survival and long-term outcomes, in patients with anti-GBM disease.
Study designRetrospective single-center case series.
MethodsAll patients diagnosed with anti-GBM disease at a major Portuguese university hospital between 2003 and 2023 were included. Anti-GBM disease was defined as a compatible clinical presentation plus positive anti-GBM antibodies in circulation and/or biopsy-proven anti-GBM disease. Demographic, clinical, laboratory and therapeutic data were reviewed.
ResultsTwenty-seven patients were included (mean age 58.7±22.0 years; 59.3% female). Renal involvement was universal and severe (mean serum creatinine 11.95±10.18mg/dL), with 92.6% requiring renal replacement therapy (RRT) at presentation. Alveolar hemorrhage occurred in 33.3% patients. Anti-GBM antibodies were detected in 92.6%; 29.6% were also ANCA-positive. Kidney biopsy (n=15) showed crescentic glomerulonephritis in 80% with a mean crescent burden of 60.9% and a median of 0% normal glomeruli (IQR 0–1). Most patients (92%) received immunosuppressive therapy, and 68% were treated with the standard combination of corticosteroids, cyclophosphamide, and plasma exchange. Renal recovery was limited: only 5 patients (18.5%) who required RRT at presentation recovered renal function, and 66.7% progressed to end-stage kidney disease (ESKD). Higher baseline serum creatinine, a lower proportion of normal glomeruli, and crescentic involvement >40% were significantly associated with ESKD. One- and five-year patient survival were 85.2% and 74.1%, respectively. No relapses occurred.
ConclusionsAnti-GBM disease in this Portuguese cohort presented predominantly with severe acute kidney injury requiring RRT and was associated with poor renal recovery despite guideline-directed therapy. Histologic preservation of normal glomeruli and baseline kidney function were strongly associated with renal outcomes. These findings underscore the need for earlier recognition and timely referral, as well as the development of more effective targeted therapies for this severe glomerular disease.
La enfermedad por anticuerpos contra la membrana basal glomerular (anti-MBG) es un trastorno autoinmune infrecuente caracterizado por autoanticuerpos dirigidos contra antígenos de las membranas basales glomerular y alveolar, que a menudo ocasiona glomerulonefritis rápidamente progresiva y hemorragia pulmonar. Los datos contemporáneos de práctica clínica real sobre la presentación clínica y los desenlaces renales a largo plazo siguen siendo limitados. El objetivo de este estudio fue describir las características clínicas y patológicas, así como la supervivencia renal y los desenlaces a largo plazo, en pacientes con enfermedad anti-MBG.
Diseño del estudioSerie de casos retrospectiva de un único centro.
MétodosSe incluyeron todos los pacientes diagnosticados de enfermedad anti-MBG en un hospital universitario portugués de referencia entre 2003 y 2023. La enfermedad anti-MBG se definió como una presentación clínica compatible junto con anticuerpos anti-MBG positivos en circulación y/o confirmación histológica mediante biopsia renal. Se revisaron los datos demográficos, clínicos, analíticos y terapéuticos.
ResultadosSe incluyeron 27 pacientes (edad media 58,7±22,0 años; 59,3% mujeres). La afectación renal fue universal y grave (creatinina sérica media 11,95±10,18mg/dL), y el 92,6% requirió terapia de reemplazo renal (TRR) al ingreso. La hemorragia alveolar se observó en el 33,3% de los pacientes. Los anticuerpos anti-MBG se detectaron en el 92,6%; el 29,6% presentó además positividad para ANCA. La biopsia renal (n=15) mostró glomerulonefritis crescentica en el 80%, con una carga media de semilunas del 60,9% y una mediana del 0% de glomérulos normales (RIC 0–1). La mayoría de los pacientes (92%) recibió tratamiento inmunosupresor, y el 68% fue tratado con la combinación estándar de corticoides, ciclofosfamida e intercambio plasmático. La recuperación renal fue limitada: solo 5 pacientes (18,5%) que requirieron TRR al ingreso recuperaron la función renal, y el 66,7% progresó a enfermedad renal terminal (ERT). Una creatinina al ingreso más elevada, una menor proporción de glomérulos normales y una afectación por semilunas>40% se asociaron significativamente con ERT. La supervivencia de los pacientes al año y a los cinco años fue del 85,2% y 74,1%, respectivamente. No se observaron recaídas.
ConclusionesEn esta cohorte portuguesa, la enfermedad anti-MBG se presentó predominantemente con lesión renal aguda grave que requirió TRR y se asoció con una escasa recuperación renal pese al tratamiento conforme a las guías. La preservación histológica de glomérulos normales y la función renal basal se asociaron estrechamente con los desenlaces renales. Estos hallazgos subrayan la necesidad de un reconocimiento más precoz y una remisión temprana, así como el desarrollo de terapias dirigidas más eficaces para esta grave enfermedad glomerular.
.
Anti-glomerular basement membrane (anti-GBM) disease is a rare, organ-specific autoimmune vasculitis targeting small vessels, mainly glomerular and, in many cases, alveolar capillaries. Its annual incidence of 0.5–1.5 cases per million and its classically bimodal age distribution underscore the rarity and heterogeneity of the condition.1–4 Pathogenesis is driven by autoantibodies directed against the non-collagenous (NC1) domain of the α3 chain of type IV collagen, leading to necrotizing and crescentic glomerulonephritis (GN) characterized by linear IgG deposition along the glomerular basement membrane (GBM).1,5,6 Approximately 80% of patients exhibit crescents involving at least half of their glomeruli.5,6
Clinically, anti-GBM disease typically presents as rapidly progressive glomerulonephritis (RPGN) with acute kidney injury (AKI) and may be accompanied by diffuse alveolar hemorrhage, occurring in 40–60% of cases and defining Goodpasture's syndrome.2,4,7 Severe manifestations are frequent: one Spanish cohort reported dialysis requirement at presentation in 84.7% of patients,1 similar to a French multicenter study in which 78% required renal replacement therapy (RRT) at diagnosis.8 These data illustrate the degree of renal involvement at disease onset.
The current standard of care combines plasma exchange (PLEX), corticosteroids (CS), and cyclophosphamide (CP) to remove circulating antibodies and suppress ongoing inflammation.2,4 Although survival has improved with modern immunosuppression (IS), intensive care support, and earlier diagnosis, renal recovery remains uncommon in patients with extensive crescentic involvement, oligoanuria or advanced kidney failure at presentation.1,9–11
Given the low incidence of anti-GBM disease, most available data derive from single-center or regional case series, with limited representation from several countries and healthcare systems.1,12 Recent reports from Spain, France, India, and multicenter collaborations have broadened understanding of the disease's clinical spectrum.1,8,12 However, no case series have been published from Portugal, where data remain restricted to isolated case reports.13 Contemporary real-world cohorts from underrepresented regions are essential to characterize epidemiology, clinical heterogeneity, response to treatment and outcomes.
In this context, we present the first contemporary Portuguese case series of anti-GBM disease from a large university hospital, describing clinical and pathological features as well as short- and long-term renal outcomes in this severe autoimmune disorder.
MethodsStudy design and settingWe conducted a retrospective, observational, single-center study of all patients diagnosed with anti-GBM disease at the Unidade Local de Saúde São João (ULSSJ), Porto, between January 2003 and December 2023. Follow-up was updated through January 2025.
Case identification and diagnostic criteriaAnti-GBM disease was defined by a compatible clinical presentation plus the presence of circulating anti-GBM antibodies and/or biopsy-proven crescentic GN with linear IgG deposition along the GBM on immunofluorescence (IF). Immunofluorescence findings were evaluated by an experienced renal pathologist and linear IgG deposition was assessed semi-quantitatively using a standard 0–3+ grading scale. Patients with dual positivity for anti-GBM antibodies and ANCA (MPO or PR3) were included if they lacked clinical features of systemic vasculitis. Individuals with isolated ANCA positivity in the absence of circulating anti-GBM antibodies or linear GBM staining were excluded, as they did not fulfill established diagnostic criteria for anti-GBM disease.
Circulating anti-GBM antibodies were measured by fluorometric enzyme immunoassay (FEIA) using manufacturer-standardized units (U/mL). Values >8U/mL were considered positive according to the validated cut-off applied at our institution during the study period. ANCA testing was performed by antigen-specific ELISA for MPO and PR3.
Data collectionDemographic, clinical, laboratory and therapeutic data were obtained from electronic medical records. Baseline variables included demographics; symptoms at presentation; AKI severity; presence of RPGN features; serum creatinine (sCr); estimated glomerular filtration rate (eGFR) calculated using the 2009 CKD-EPI equation; proteinuria (g/24h); anti-GBM and ANCA serology; and need for renal replacement therapy (RRT). Therapeutic data included use and route of CS and CP, number of PLEX sessions and Intensive Care Unit (ICU) admissions. Corticosteroid therapy typically consisted of intravenous methylprednisolone pulses followed by oral prednisone. Cyclophosphamide was administered either intravenously or orally according to standard regimens. Plasmapheresis was performed with albumin replacement (fresh frozen plasma if alveolar hemorrhage), daily, using one plasma-volume exchange, until antibody negativation and when indicated according to KDIGO guidelines. Overall and renal survival, relapse events, and kidney transplantation status were collected up to January 2025.
Kidney histopathologyKidney biopsy was processed for optic microscopy (OM) using routine staining (H&E, PAS, silver, Masson). IF studies included staining for IgG, IgA, IgM, C3, C1q, κ, and λ. Histologic variables collected included total number of glomeruli; percentage of normal glomeruli; crescent type and proportion; presence of fibrinoid necrosis or Bowman's capsule rupture; and degree of interstitial fibrosis and tubular atrophy (IFTA). Electron microscopy was not routinely performed.
DefinitionsSeveral operational definitions were applied to ensure consistency in the characterization of clinical and renal outcomes. RRT at presentation referred to the initiation of dialysis within 72h of hospital admission. End-stage kidney disease (ESKD) was defined as persistent dialysis dependence without subsequent renal recovery. Renal recovery was considered in patients who were initially dialysis-dependent and subsequently remained dialysis-independent for at least 12 weeks during follow-up. Patient survival was defined as time from diagnosis to death from any cause. Renal survival was defined as the time from diagnosis to initiation of RRT.
Crescentic GN was defined as crescents involving ≥50% of glomeruli. RPGN was defined by rapidly worsening kidney function accompanied by an active urinary sediment and/or crescentic GN on kidney biopsy. Pulmonary hemorrhage was diagnosed based on overt hemoptysis and/or radiologic evidence of alveolar hemorrhage on chest computed tomography (CT). Relapse was defined as pulmonary or renal deterioration occurring more than three months after diagnosis, in association with rising anti-GBM antibody titers and/or biopsy evidence of active GN, as defined by Marques et al.8 Normal glomeruli were defined histologically as glomeruli without crescents, fibrinoid necrosis, or chronic scarring.
Statistical analysisContinuous variables were expressed as mean±SD (standard deviation) or median (interquartile range, IQR), according to distribution. Categorical variables were summarized as absolute and relative frequencies. Group comparisons used chi-square or Fisher's exact test for categorical variables, and Student's t-test or Mann–Whitney test for continuous variables. Survival analysis was performed using Kaplan–Meier curves and the log-rank test after stratification according to predefined clinical and histopathological variables. Statistical significance was defined as p<0.05. Analyses were conducted using IBM SPSS Statistics version 28.0.
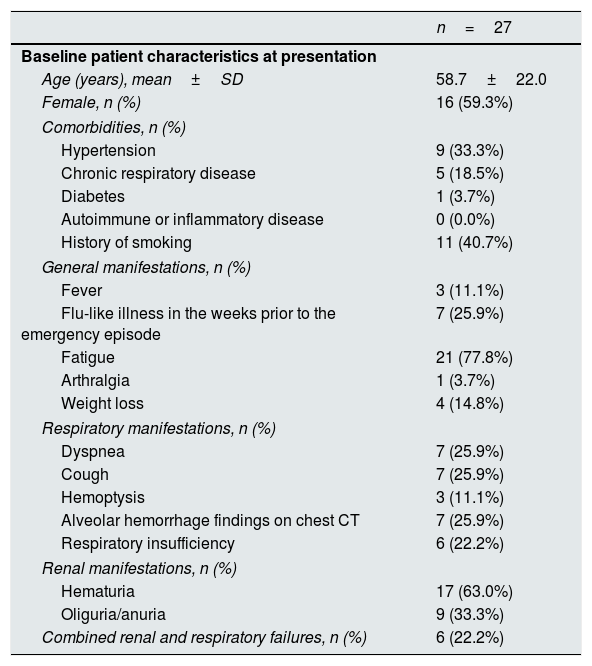
ResultsBaseline characteristics and clinical presentationA total of 27 patients met diagnostic criteria for anti-GBM disease. The mean age at presentation was 58.7±22.0 years and 59.3% were female. Hypertension was present in 33.3% of patients, while 40.7% had a history of smoking. No patient had a previous autoimmune or chronic inflammatory disorder. Baseline demographic and clinical characteristics are summarized in Table 1.
Demographic and clinical characteristics of patients with anti-GBM disease.
| n=27 | |
|---|---|
| Baseline patient characteristics at presentation | |
| Age (years), mean±SD | 58.7±22.0 |
| Female, n (%) | 16 (59.3%) |
| Comorbidities, n (%) | |
| Hypertension | 9 (33.3%) |
| Chronic respiratory disease | 5 (18.5%) |
| Diabetes | 1 (3.7%) |
| Autoimmune or inflammatory disease | 0 (0.0%) |
| History of smoking | 11 (40.7%) |
| General manifestations, n (%) | |
| Fever | 3 (11.1%) |
| Flu-like illness in the weeks prior to the emergency episode | 7 (25.9%) |
| Fatigue | 21 (77.8%) |
| Arthralgia | 1 (3.7%) |
| Weight loss | 4 (14.8%) |
| Respiratory manifestations, n (%) | |
| Dyspnea | 7 (25.9%) |
| Cough | 7 (25.9%) |
| Hemoptysis | 3 (11.1%) |
| Alveolar hemorrhage findings on chest CT | 7 (25.9%) |
| Respiratory insufficiency | 6 (22.2%) |
| Renal manifestations, n (%) | |
| Hematuria | 17 (63.0%) |
| Oliguria/anuria | 9 (33.3%) |
| Combined renal and respiratory failures, n (%) | 6 (22.2%) |
Abbreviations: GBM, glomerular basement membrane; SD, standard deviation.
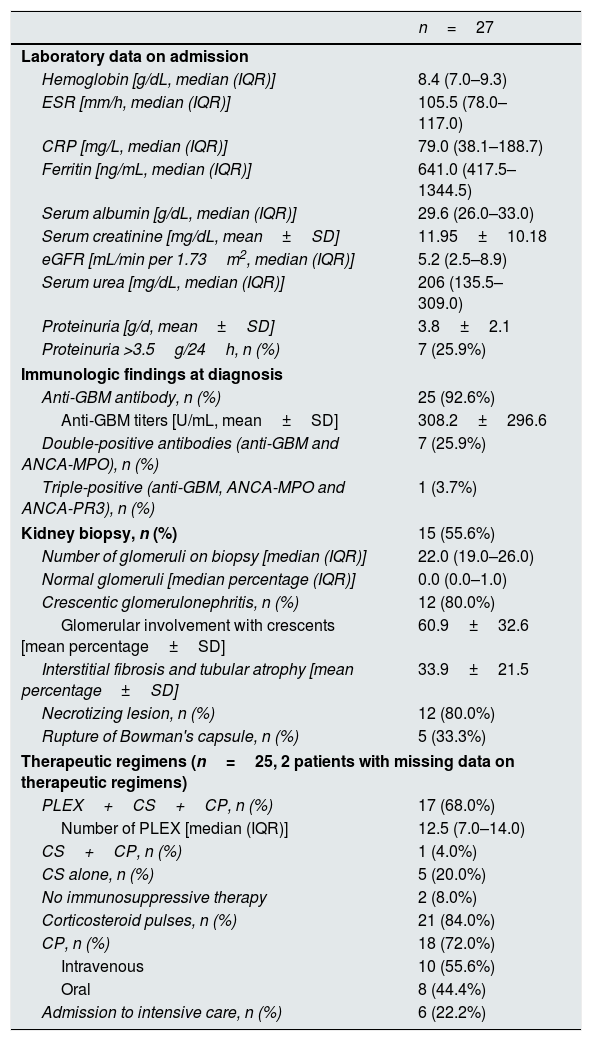
Fatigue was the most frequently reported symptom (77.8%), followed by oliguria or anuria (33.3%), hematuria (63.0%) and respiratory complaints such as dyspnea or cough (25.9%). Flu-like symptoms in the preceding weeks were recalled by 25.9% of patients, while fever, arthralgia, and weight loss were less common.
Pulmonary involvement consistent with alveolar hemorrhage was present in 9 patients (33.3%). An additional 5 patients (18.5%) displayed non-specific pulmonary abnormalities on chest CT, including ground-glass opacities or features suggestive of infection or bronchiectasis, but without evidence of alveolar hemorrhage. Respiratory failure occurred in 6 patients (22.2%), four of whom had confirmed alveolar hemorrhage.
All patients exhibited renal involvement. Mean serum creatinine at presentation was 11.95±10.18mg/dL, corresponding to an eGFR of 5.2mL/min/1.73m2 (IQR 2.5–8.9). The mean 24-h proteinuria was 3.8±2.1g/day, with nephrotic-range proteinuria detected in 7 patients (25.9%). Laboratory and histopathologic features are summarized in Table 2.
Laboratory, histopathologic, and therapeutic characteristics of patients with anti-GBM disease.
| n=27 | |
|---|---|
| Laboratory data on admission | |
| Hemoglobin [g/dL, median (IQR)] | 8.4 (7.0–9.3) |
| ESR [mm/h, median (IQR)] | 105.5 (78.0–117.0) |
| CRP [mg/L, median (IQR)] | 79.0 (38.1–188.7) |
| Ferritin [ng/mL, median (IQR)] | 641.0 (417.5–1344.5) |
| Serum albumin [g/dL, median (IQR)] | 29.6 (26.0–33.0) |
| Serum creatinine [mg/dL, mean±SD] | 11.95±10.18 |
| eGFR [mL/min per 1.73m2, median (IQR)] | 5.2 (2.5–8.9) |
| Serum urea [mg/dL, median (IQR)] | 206 (135.5–309.0) |
| Proteinuria [g/d, mean±SD] | 3.8±2.1 |
| Proteinuria >3.5g/24h, n (%) | 7 (25.9%) |
| Immunologic findings at diagnosis | |
| Anti-GBM antibody, n (%) | 25 (92.6%) |
| Anti-GBM titers [U/mL, mean±SD] | 308.2±296.6 |
| Double-positive antibodies (anti-GBM and ANCA-MPO), n (%) | 7 (25.9%) |
| Triple-positive (anti-GBM, ANCA-MPO and ANCA-PR3), n (%) | 1 (3.7%) |
| Kidney biopsy, n (%) | 15 (55.6%) |
| Number of glomeruli on biopsy [median (IQR)] | 22.0 (19.0–26.0) |
| Normal glomeruli [median percentage (IQR)] | 0.0 (0.0–1.0) |
| Crescentic glomerulonephritis, n (%) | 12 (80.0%) |
| Glomerular involvement with crescents [mean percentage±SD] | 60.9±32.6 |
| Interstitial fibrosis and tubular atrophy [mean percentage±SD] | 33.9±21.5 |
| Necrotizing lesion, n (%) | 12 (80.0%) |
| Rupture of Bowman's capsule, n (%) | 5 (33.3%) |
| Therapeutic regimens (n=25, 2 patients with missing data on therapeutic regimens) | |
| PLEX+CS+CP, n (%) | 17 (68.0%) |
| Number of PLEX [median (IQR)] | 12.5 (7.0–14.0) |
| CS+CP, n (%) | 1 (4.0%) |
| CS alone, n (%) | 5 (20.0%) |
| No immunosuppressive therapy | 2 (8.0%) |
| Corticosteroid pulses, n (%) | 21 (84.0%) |
| CP, n (%) | 18 (72.0%) |
| Intravenous | 10 (55.6%) |
| Oral | 8 (44.4%) |
| Admission to intensive care, n (%) | 6 (22.2%) |
Abbreviations: CP, cyclophosphamide; CRP, C-reactive protein; CS, corticosteroids; CT, computed tomography; eGFR, estimated glomerular filtration rate; ESR, erythrocyte sedimentation rate; GBM, glomerular basement membrane; IQR, interquartile range; MPO, myeloperoxidase; PLEX, plasma exchange; PR3, proteinase 3; SD, standard deviation.
Circulating anti-GBM antibodies were detected in 25 patients (92.6%), with a mean titer of 308.2±296.6U/mL; 17 (70.8%) had titers >100U/mL. The median time to anti-GBM antibodies clearance was 17 days (IQR 14–21). Concurrent ANCAs with MPO specificity were identified in 8 patients (29.6%), including one with dual MPO and PR3 positivity. Two patients (7.4%) were anti-GBM seronegative and were diagnosed based on a compatible clinical presentation and biopsy-proven crescentic glomerulonephritis with diffuse linear IgG deposition along the GBM, after exclusion of alternative causes of linear IgG staining. Neither of these last patients had diabetes mellitus. All patients tested negative for hepatitis B and C, EBV, and CMV.
Kidney histopathologyKidney biopsy was performed in 15 patients (55.6%). A median of 22 glomeruli (IQR 19–26) was available per specimen. Crescentic GN was present in 12 patients (80%). The mean percentage of crescents across all biopsies was 60.9±32.6%, predominantly cellular, with fewer fibrocellular crescents. Fibrinoid necrosis and Bowman's capsule rupture were identified in 80.0% and 33.3% of patients, respectively. IFTA was present in most biopsies with a mean involvement of 33.9±21.5%. The percentage of normal glomeruli was low with a median of 0% (IQR 0–1). IF demonstrated linear IgG deposition in 12 of 14 evaluable biopsies; the two patients without linear IgG staining had pauci-immune patterns. PLA2R staining was positive in 1 of the 2 patients evaluated.
TreatmentTherapeutic data were available for 25 patients. Twenty-three (92%) received immunosuppressive therapy most commonly the combination of CS, CP, and PLEX (68%). The median number of PLEX sessions was 12.5 (IQR 7–14). Corticosteroid pulses were administered in 84%, and CP was given intravenously in 10 patients (40%) and orally in 8 (32%). Immunosuppressive therapy and PLEX were withheld in 2 patients due to extended chronicity and absence of pulmonary involvement. Six patients (22.2%) required ICU admission during the acute presentation.
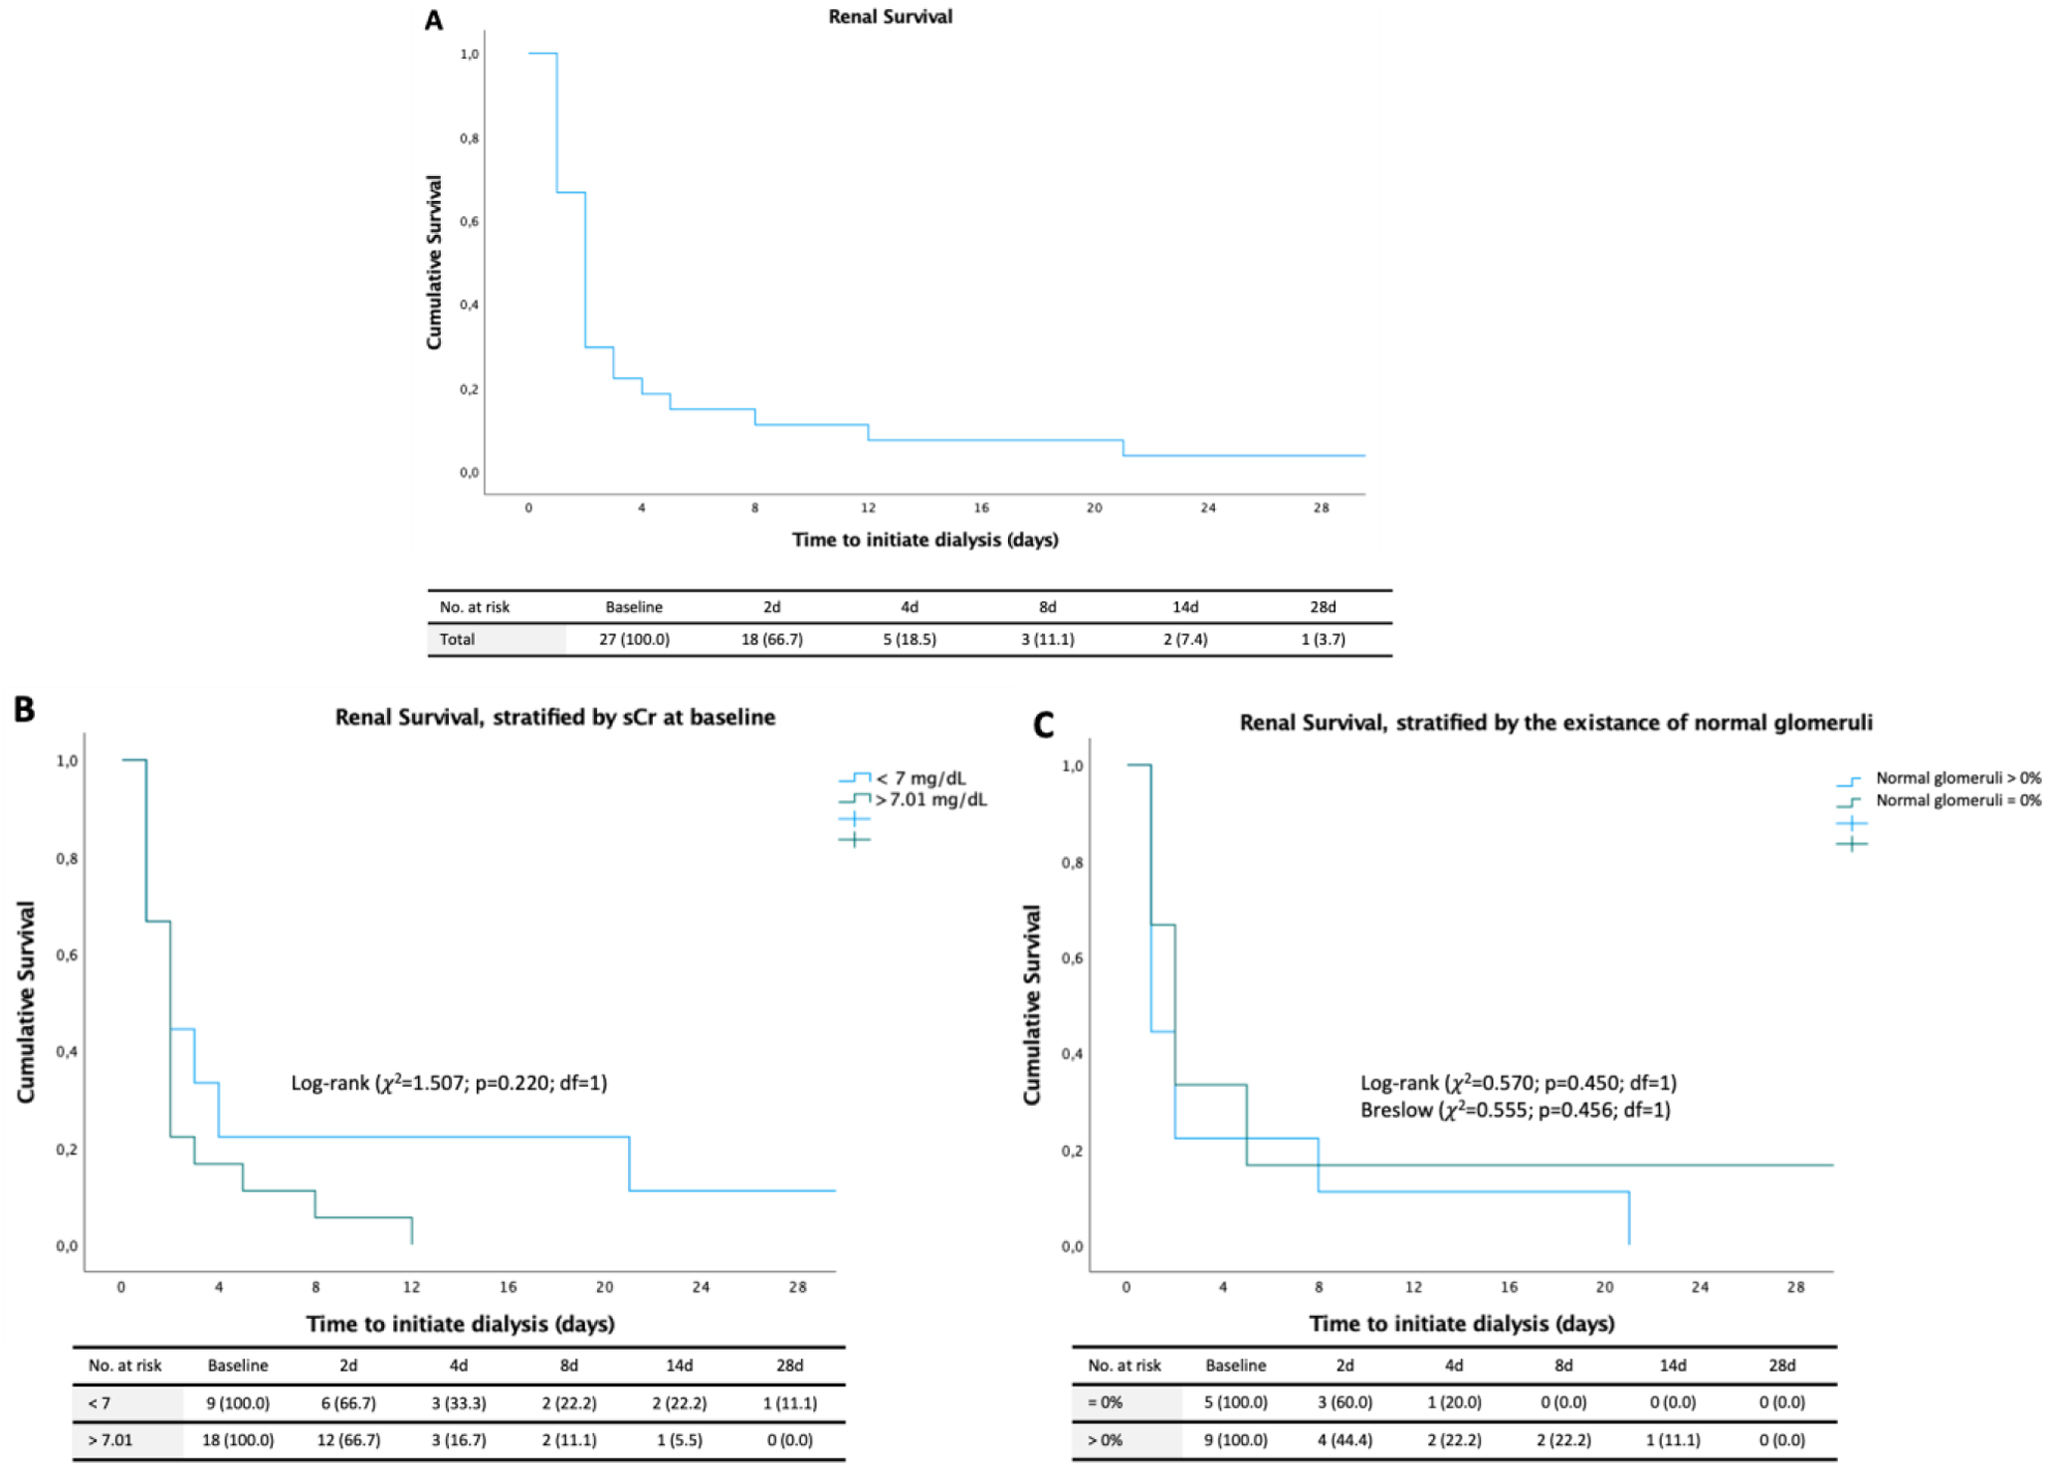
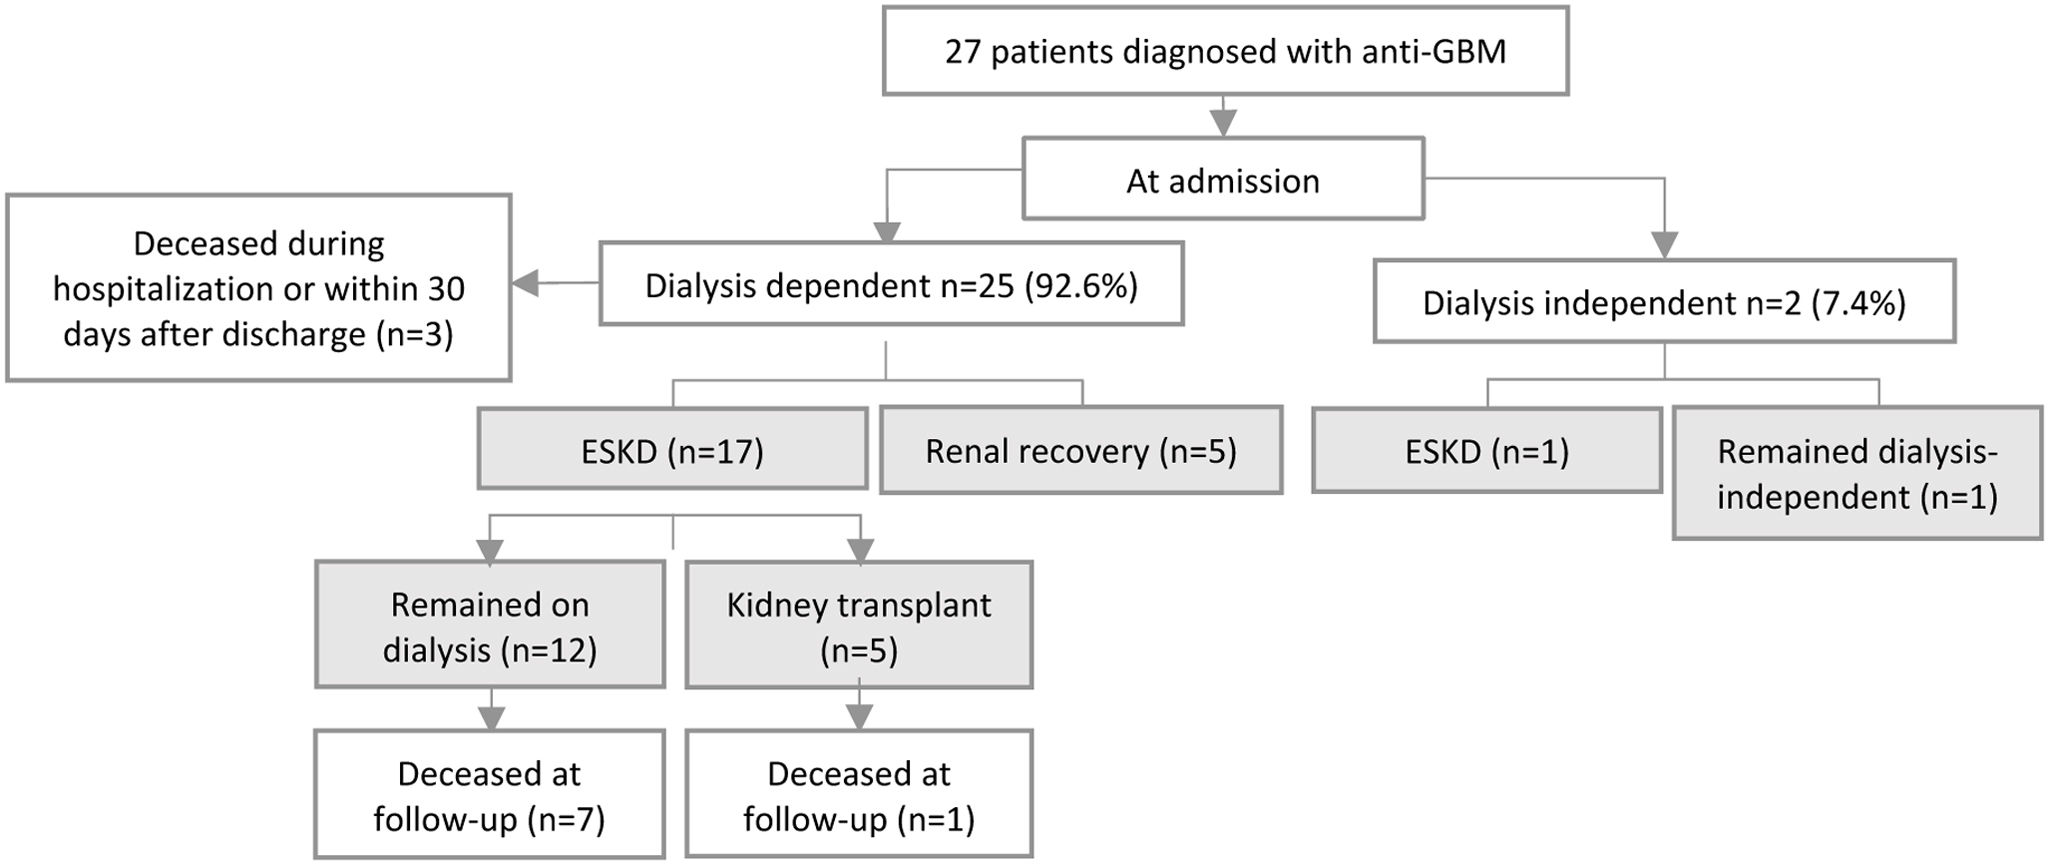
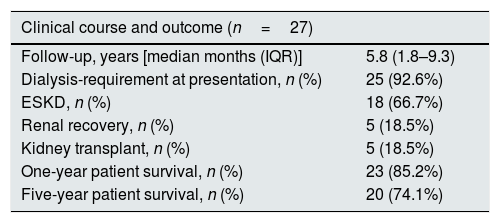
Renal outcomesAt presentation, 25 patients (92.6%) required RRT shortly after admission (Fig. 1). Among these, 5 patients (18.5%) recovered kidney function within the first 6 months (median time to dialysis independence, 34 days [IQR 25–64]), while 17 progressed to ESKD. One additional patient who initially did not require RRT subsequently progressed to ESKD within the first month, resulting in a total of 18 patients (66.7%) reaching ESKD. Only one patient remained dialysis-independent throughout the entire follow-up; this individual had anti-GBM positivity, alveolar hemorrhage, mild kidney impairment and linear IgG deposition along the glomerular basement membrane without crescents. The overall clinical course is summarized in Table 3 and patient trajectories are depicted in Fig. 2.

Kaplan–Meier estimates of renal survival in patients with anti-GBM disease (A), stratified according to baseline serum creatinine (B) and the presence of normal glomeruli on kidney biopsy (C). Results of univariate analyses using the log-rank test are shown for each variable. Renal recovery occurred in 5 patients (median time to dialysis independence, 34 days [IQR 25–64]). Abbreviations: IQR, interquartile range; sCR, serum creatinine.
Clinical course and outcome of patients with anti-GBM.
| Clinical course and outcome (n=27) | |
|---|---|
| Follow-up, years [median months (IQR)] | 5.8 (1.8–9.3) |
| Dialysis-requirement at presentation, n (%) | 25 (92.6%) |
| ESKD, n (%) | 18 (66.7%) |
| Renal recovery, n (%) | 5 (18.5%) |
| Kidney transplant, n (%) | 5 (18.5%) |
| One-year patient survival, n (%) | 23 (85.2%) |
| Five-year patient survival, n (%) | 20 (74.1%) |
Abbreviations: ESKD, end-stage kidney disease; GBM, glomerular basement membrane; IQR, interquartile range.

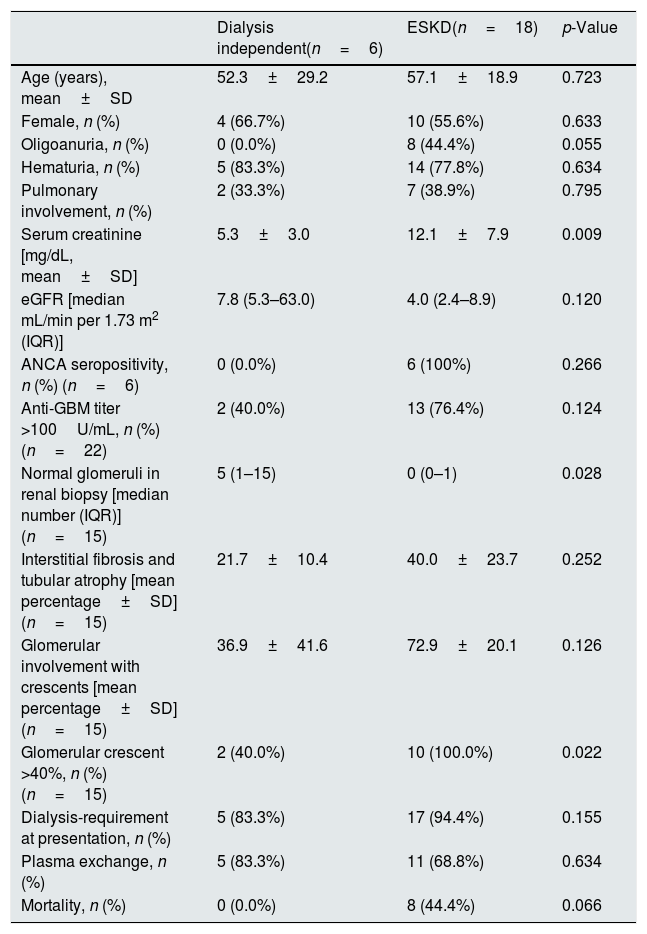
Renal outcomes at 6 months were further analyzed by comparing dialysis-independent patients (n=6) with those who progressed to ESKD (n=18), as shown in Table 4. Patients who developed ESKD had higher serum creatinine at presentation (12.1±7.9 vs. 5.3±3.0mg/dL; p=0.009), fewer normal glomeruli (0% vs. 5%; p=0.028), and more frequent crescentic involvement >40% (66.7% vs. 13.3%; p=0.022). Although the mean percentage of crescents was higher in the ESKD group, this difference was not statistically significant. High anti-GBM antibody titers also showed a trend toward worse renal outcomes: both patients who died early had titers >100U/mL, and all patients with titers above this threshold required dialysis at presentation. High titers (>100U/mL) were more common among patients who progressed to ESKD (76.4% vs. 40.0%), although this association did not reach statistical significance.
Baseline characteristics and clinical outcomes based on progression to end-stage kidney disease in anti-GBM Disease.
| Dialysis independent(n=6) | ESKD(n=18) | p-Value | |
|---|---|---|---|
| Age (years), mean±SD | 52.3±29.2 | 57.1±18.9 | 0.723 |
| Female, n (%) | 4 (66.7%) | 10 (55.6%) | 0.633 |
| Oligoanuria, n (%) | 0 (0.0%) | 8 (44.4%) | 0.055 |
| Hematuria, n (%) | 5 (83.3%) | 14 (77.8%) | 0.634 |
| Pulmonary involvement, n (%) | 2 (33.3%) | 7 (38.9%) | 0.795 |
| Serum creatinine [mg/dL, mean±SD] | 5.3±3.0 | 12.1±7.9 | 0.009 |
| eGFR [median mL/min per 1.73 m2 (IQR)] | 7.8 (5.3–63.0) | 4.0 (2.4–8.9) | 0.120 |
| ANCA seropositivity, n (%) (n=6) | 0 (0.0%) | 6 (100%) | 0.266 |
| Anti-GBM titer >100U/mL, n (%) (n=22) | 2 (40.0%) | 13 (76.4%) | 0.124 |
| Normal glomeruli in renal biopsy [median number (IQR)] (n=15) | 5 (1–15) | 0 (0–1) | 0.028 |
| Interstitial fibrosis and tubular atrophy [mean percentage±SD] (n=15) | 21.7±10.4 | 40.0±23.7 | 0.252 |
| Glomerular involvement with crescents [mean percentage±SD] (n=15) | 36.9±41.6 | 72.9±20.1 | 0.126 |
| Glomerular crescent >40%, n (%) (n=15) | 2 (40.0%) | 10 (100.0%) | 0.022 |
| Dialysis-requirement at presentation, n (%) | 5 (83.3%) | 17 (94.4%) | 0.155 |
| Plasma exchange, n (%) | 5 (83.3%) | 11 (68.8%) | 0.634 |
| Mortality, n (%) | 0 (0.0%) | 8 (44.4%) | 0.066 |
Abbreviations: eGFR, estimated glomerular filtration rate; GBM, glomerular basement membrane; IQR, interquartile range.
All 9 patients who presented with pulmonary-renal syndrome experienced resolution of alveolar hemorrhage; however, only two recovered kidney function. ANCA status did not correlate with renal survival; among the 6 surviving ANCA-positive patients, all ultimately progressed to ESKD.
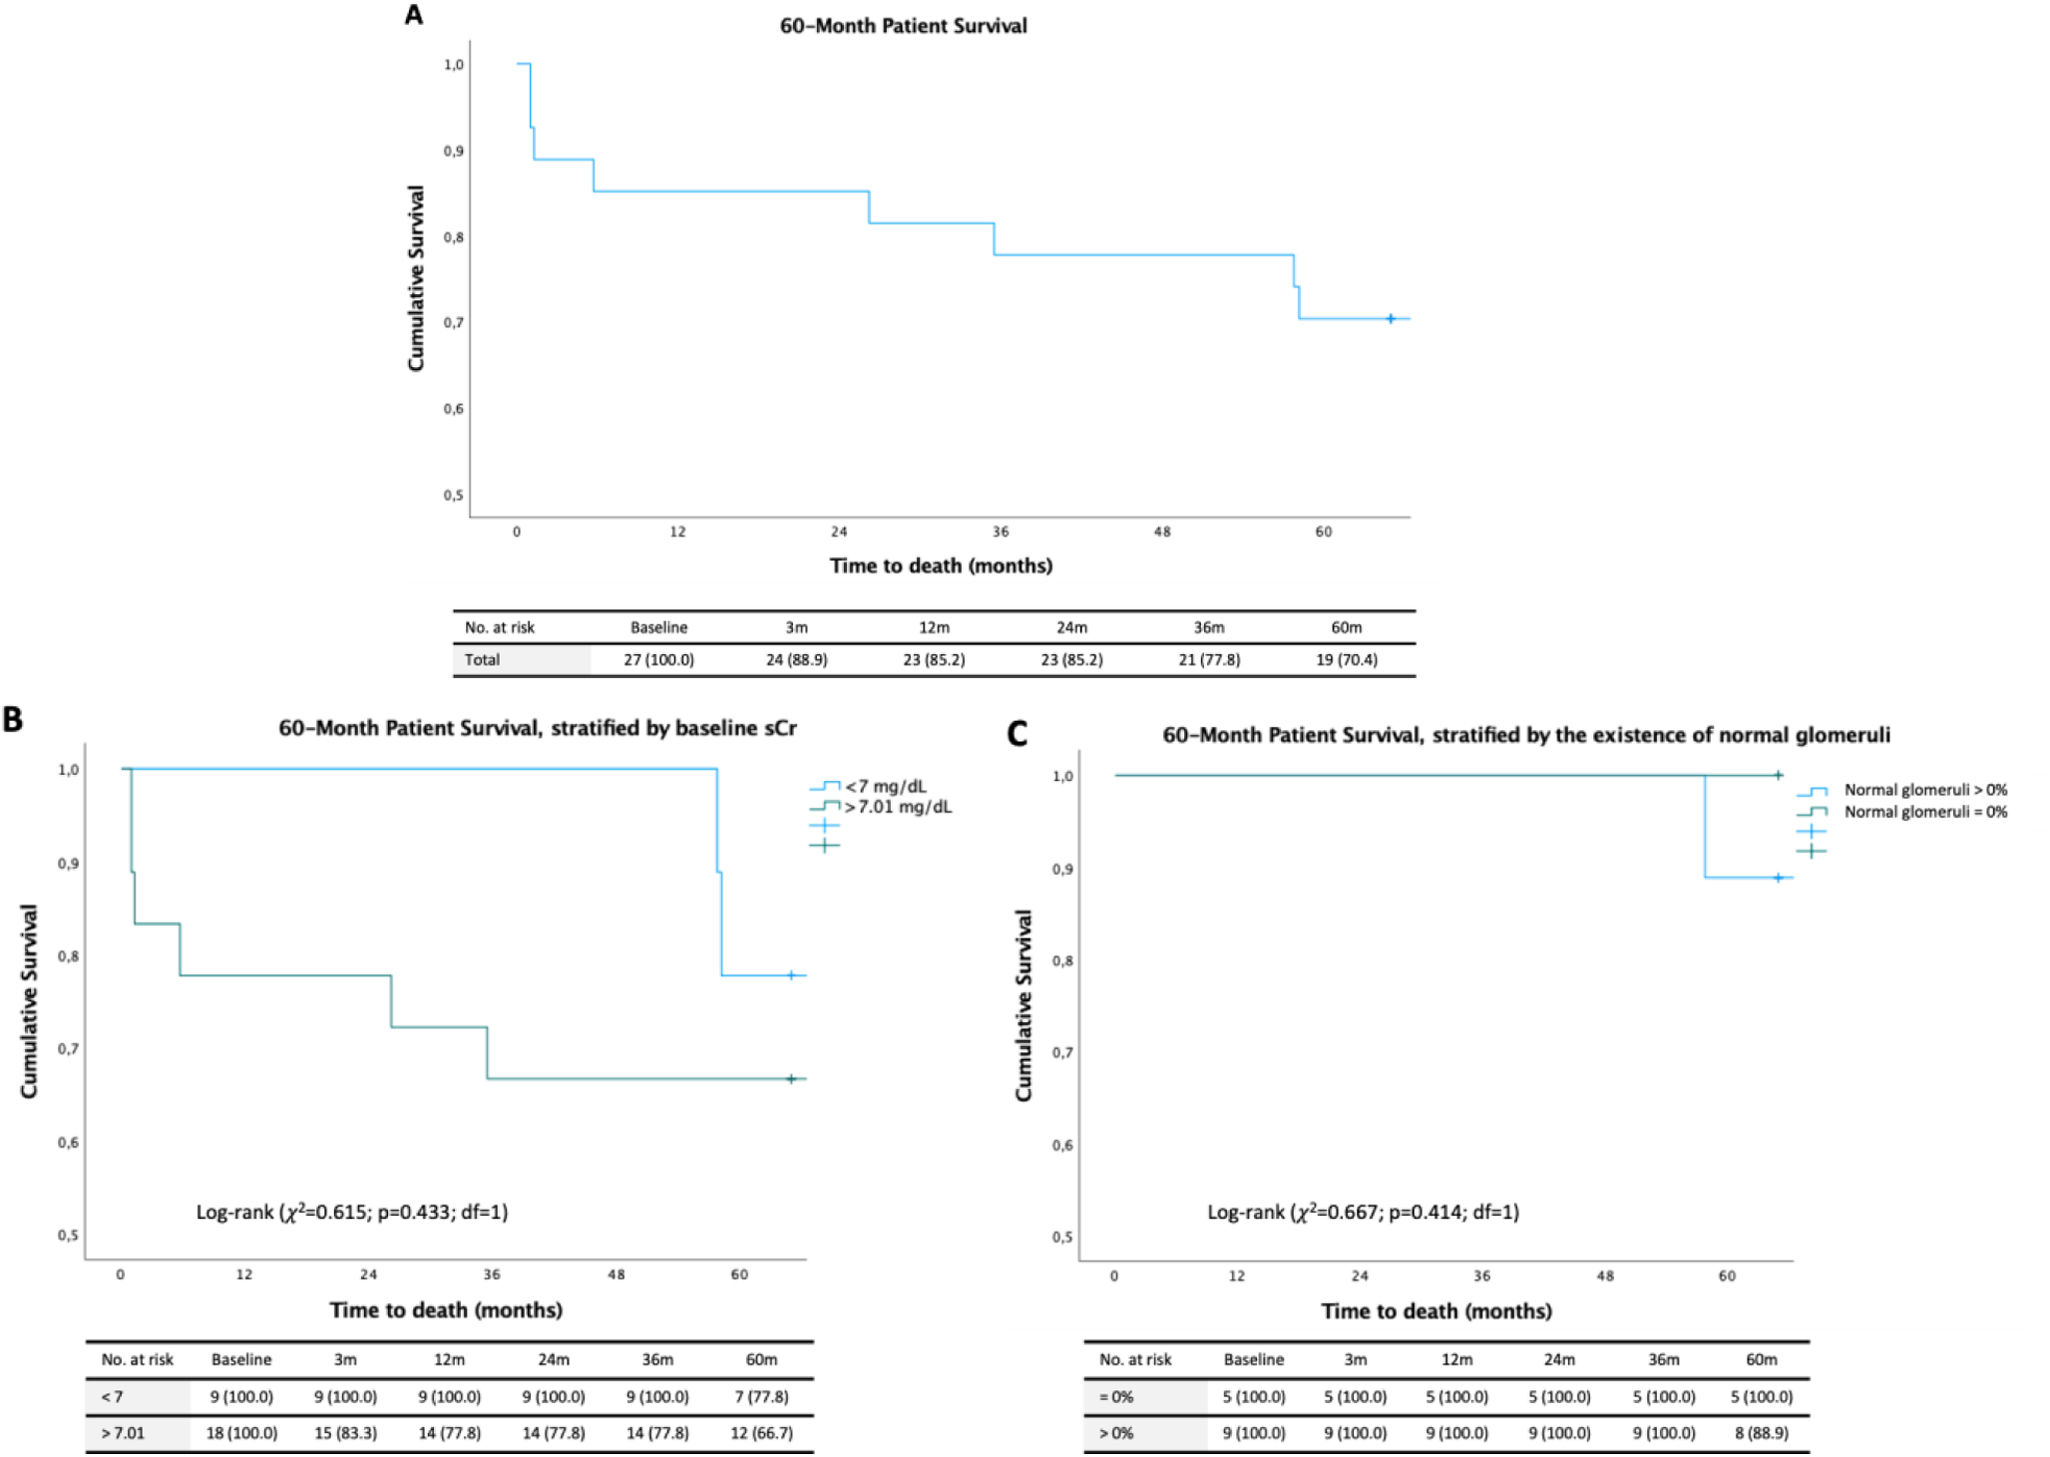
Patient outcomesOverall patient survival at 1, 3 and 5 years was 85.2% (95% CI, 71.8–98.6%), 77.8% (95% CI, 62.1–93.5%), and 74.1% (95% CI, 57.5–90.6%), respectively. Three patients (11.1%) died during hospitalization or within 30 days of discharge. During long-term follow-up, 8 patients (33.3%) died (median time to death of 35.5 months). Patient survival did not differ significantly according to baseline serum creatinine or the presence of normal glomeruli on kidney biopsy (Fig. 3).

Five patients (18.5%) received a kidney transplant. No graft failure was observed during follow-up; one patient died seven years post-transplantation with a functioning graft. No cases of recurrent anti-GBM disease were observed.
DiscussionAnti-GBM disease remains a severe condition associated with substantial renal morbidity and non-negligible mortality.4 This study provides the first contemporary description of anti-GBM disease from a Portuguese cohort and offers insights into its clinical presentation, histopathologic features and outcomes over two decades of real-world practice.
The demographic profile of our cohort aligns with reports from Spain, India, and France, with a mean age near 60 years and a slight female predominance.1,3,8 Unlike the bimodal age distribution described in larger studies,1,14 our population exhibited a unimodal distribution skewed toward older adults, likely reflecting the small sample size and potentially a lower detection rate of mild disease in younger individuals.
The clinical presentation in our cohort was dominated by nonspecific symptoms such as fatigue, malaise, or constitutional complaints, reported by nearly 80% of patients. One-quarter of patients recalled a recent flu-like illness, consistent with previous observations suggesting that upper respiratory infections may precede disease onset.4,15
Pulmonary involvement was documented in one-third of patients, comparable to the 25–30% prevalence described in prior cohorts.4 Among those with alveolar hemorrhage, nearly half developed respiratory failure, a pattern similar to earlier series reporting severe respiratory compromise in up to 50% of affected individuals.16 An additional subset of patients (18.5%) demonstrated non-specific pulmonary abnormalities, which may reflect concurrent infection or inflammatory changes rather than overt hemorrhage.5
Renal involvement was universal and typically severe. Almost all patients presented with AKI compatible with RPGN and more than 90% required RRT at admission, an even higher proportion than that reported in the Spanish (84.7%) and French cohorts (78%)1,8 (Supplementary Table 1). Renal recovery was rare: only five of the 25 dialysis-dependent patients at admission regained kidney function and two-thirds of the overall cohort progressed to ESKD. These findings parallel previous studies in which 1-year kidney survival among patients requiring dialysis at presentation remains consistently low (8–37.5%).1,9,17–19
Several clinical, biochemical and histologic features have been associated with poor kidney survival in anti-GBM disease. Dialysis dependence at presentation, oligoanuria, elevated serum creatinine, and extensive crescentic involvement are consistently reported as strong adverse prognostic indicators.1,8,9,20 Our findings were consistent with these observations, as patients who progressed to ESKD had significantly higher serum creatinine at admission. Histopathologic evaluation confirmed severe glomerular injury, with crescentic GN present in 80% of biopsied patients and a mean crescent burden of 60.9%. The proportion of normal glomeruli, a key prognostic variable identified in recent large cohorts,11,18 was extremely low in our series and significantly differed between patients who progressed to ESKD and those who remained dialysis-independent. A crescentic burden >40% was also associated with poorer outcomes. In contrast with previous observations in which severe IFTA was identified as an independent predictor of poor renal survival,17 the degree of IFTA did not differ significantly between groups, possibly reflecting limited biopsy availability and sampling variability.
Double positivity for anti-GBM antibodies and ANCA was observed in 33% of patients, consistent with previous reports.8,9 The clinical relevance of dual seropositivity remains debatable, with previous studies reporting conflicting outcomes. While some cohorts suggest improved survival or higher likelihood of renal recovery in double-positive patients,21,22 others report similar or even worse renal outcomes compared to anti-GBM single-positive patients.9,20 Although ANCA status was not statistically associated with renal outcomes, all surviving double-positive patients progressed to ESKD, supporting the notion that dual seropositivity may reflect a more prolonged disease process at diagnosis and more extensive glomerular injury. Olson et al. propose that ANCA-induced glomerular inflammation may serve as a trigger for the development of an anti-GBM immune response by modifying or unmasking normally sequestered epitopes within the GBM, as supported by the observation that ANCA may be detected prior to the onset of anti-GBM disease in some patients.23
Historically, anti-GBM disease was associated with extremely high mortality, with rates reaching up to 95% in early series.24 The introduction of combined therapy with CS, CP and PLEX has markedly improved outcomes,7 although 1-year survival remains heterogeneous across contemporary cohorts with European studies reporting rates close to 90%,1,8,9 while outcomes from Asia are less favourable.17,19 In our cohort, 1- and 5-year patient survival rates were 85.2% and 74.1%, respectively, aligning with the range observed in Western series. Treatment patterns largely followed international recommendations,5 with the majority of patients receiving CS, CP and PLEX. The median number of PLEX sessions (12.5) was comparable to that reported by Huart et al., in which plasma exchange number was associated with overall survival.25 Despite adherence to standard therapy, renal outcomes remained poor, emphasizing the critical importance of early recognition and prompt intervention. Emerging therapies, such as rituximab and imlifidase, are currently under investigation and their role in anti-GBM disease has yet to be clearly defined.2,26
This study has several strengths, including a 20-year capture period, stringent diagnostic criteria for patient inclusion and long-term follow-up. However, limitations inherent to retrospective studies must be acknowledged. The sample size was small [due to the rarity of the disease], limiting statistical power. Histopathologic data were unavailable in a subset of patients and certain clinical details and longitudinal serologic data were incomplete, potentially introducing selection and information biases. The restricted availability of biopsy samples may also underrepresent patients in whom biopsy was contraindicated or advanced disease, particularly in anti-GBM seronegative cases.
In conclusion, this study provides the first detailed case series of anti-GBM disease from Portugal and highlights the severe renal presentation and high rate of progression to ESKD in this population. High serum creatinine at admission, a low proportion of normal glomeruli and crescentic involvement >40% were associated with poorer renal outcomes. These findings underscore the importance of heightened clinical suspicion, rapid diagnostic evaluation and early therapeutic intervention. Collaborative multicenter efforts and continued innovation in targeted therapies will be essential to improve outcomes in this rare and aggressive form of GN.
Conflict of interestThe authors declare no conflict of interest.
The following are the supplementary data to this article:





